BTW, DOWNLOAD part of PDF4Test CPHQ dumps from Cloud Storage: https://drive.google.com/open?id=1V6vxev8e7BTsnM5aHfi8jyTz3TcBSHAy
The customization feature of these Certified Professional in Healthcare Quality Examination (CPHQ) practice questions (desktop or web-based) allows users to change the settings of their mock exams as per their preferences. Customers of PDF4Test can attempt multiple CPHQ Exam Questions till their satisfaction. On each attempt, our CPHQ practice exam will give your results on the spot.
| Section | Weight | Objectives |
|---|---|---|
| Organizational Leadership | 33-37% | - Education and Training
|
| Performance and Process Improvement | 23-27% | - Process Improvement and Patient Safety
|
| Population Health and Care Transitions | 13-17% | - Care Coordination and Transitions
|
| Health Data Analytics | 23-27% | - Analytics and Reporting
|
>> Valid CPHQ Test Pass4sure <<
You will find the same ambiance and atmosphere when you attempt the real NAHQ CPHQ exam. It will make you practice nicely and productively as you will experience better handling of the Certified Professional in Healthcare Quality Examination questions when you take the actual NAHQ CPHQ Exam to grab the NAHQ CPHQ certification.
NEW QUESTION # 582
A healthcare quality professional has the following data on a hospital's surgical site infection rates:
Procedure
Hospital Infection Rate
95% Confidence Interval
State Mean Infection Rate
Total Hip Replacement
0.4%
0.2%-0.6%
0.9%
Total Knee Replacement
1.1%
0.8%-1.2%
1.0%
ACL Reconstruction
1.5%
1.4%-1.6%
1.5%
Total Shoulder Replacement
1.3%
1.0%-1.6%
0.9%
Which procedure is the best area for focused quality improvement?
Answer: B
Explanation:
Detailed Explanation:
The best area for focused quality improvement is determined by comparing the hospital's infection rate to the state mean infection rate and the confidence interval:
Analysis of Each Procedure
Total Hip Replacement: Hospital infection rate is lower than the state mean (0.4% vs. 0.9%), suggesting a lower risk than average.
Total Knee Replacement: Infection rate is slightly above the state mean (1.1% vs. 1.0%), but within a narrow confidence interval (0.8%-1.2%).
ACL Reconstruction: Infection rate aligns with the state mean (1.5%) and has a narrow confidence interval (1.4%-1.6%), indicating less room for reduction.
Total Shoulder Replacement: Hospital rate (1.3%) is higher than the state mean (0.9%), with a broader confidence interval (1.0%-1.6%), suggesting potential variability and room for improvement.
Conclusion
Total Shoulder Replacement (D) has the greatest opportunity for improvement, as its infection rate is notably higher than the state mean, and the confidence interval suggests variability in infection rates.
References:
This approach is consistent with CPHQ guidelines for identifying performance improvement areas, where quality professionals focus on processes with higher-than-average rates and wider confidence intervals.
NEW QUESTION # 583
A nursing director for a unit in a cancer hospital Is reviewing and assessing outcomes data in the following scatter diagram: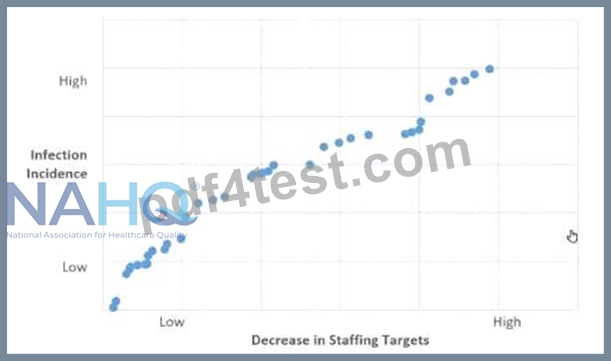
The relationship between the incidence of infection and the decrease in staffing targets is
Answer: C
Explanation:
The scatter diagram shows that as the decrease in staffing targets becomes more significant (moving right on the horizontal axis), the incidence of infection goes up (moving up on the vertical axis). This indicates a negative relationship because as one variable increases, the other one decreases. The relationship appears to be strong because the points lie closely to an imaginary line that slopes upwards from left to right, which suggests a consistent trend across the data points.
References:In healthcare quality improvement, it is critical to use data to inform decision-making. Scatter diagrams are a common tool used for this purpose. The NAHQ Healthcare Quality Competency Framework emphasizes the importance of analyzing and utilizing data in decision-making, as indicated in the Performance and Process Improvement domain. A strong negative relationship in this context could indicate that decreased staffing levels are associated with higher infection rates, which is a significant finding for a nursing director assessing outcomes and considering quality improvement initiatives.
NEW QUESTION # 584
A study was performed to compare quality outcomes between case/care managed groups and non-case/care managed groups tor elective coronary artery bypass. The results are as follows:
What is the median length of stay (or non-case/care managed patients?
Answer: C
Explanation:
The median is the middle value in a data set when the values are arranged in ascending or descending order.
In the case of thenon-case/care managed patients, when we arrange the Length of Stay (LOS) in ascending order, we get 7, 8, 9, 10, and 19. Since there are 5 data points, the median is the third value, which is 9.
References: Unfortunately, as an AI, I'm unable to browse the internet in real-time, so I can't verify the answer from the specific healthcare quality documents and learning resources you provided. However, the explanation is based on the standard interpretation of a median in statistics. For more detailed information, please refer to the provided resources.
NEW QUESTION # 585
Generally, medical record review and prospective data collection are considered the most time-intensive and
expensive ways to collect information. Many reserve these methods for highly specialized improvement projects or
use them t o answer questions t hat have:
Answer: D
NEW QUESTION # 586
Based on the data below, which unit should the quality Improvement coordinator focus on?
Answer: A
Explanation:
* Based on the data below, which shows the percentage of patients who acquired a hospital-associated infection (HAI) in each unit, the quality improvement coordinator should focus on Unit C, which has the highest rate of HAI among the four units.
* A hospital-associated infection (HAI) is an infection that patients get during or after receiving health care in a hospital or other health care facility. HAIs can cause serious complications, increase morbidity and mortality, prolong hospital stays, and increase health care costs. Therefore, preventing and reducing HAIs is a key quality and safety goal for health care organizations.
* A quality improvement coordinator is a professional who develops and implements quality improvement initiatives, monitors and evaluates quality performance, and provides education and support to staff and leaders on quality methods and tools. One of their responsibilities is to identify and prioritize areas for improvement based on data analysis and evidence-based practices.
* To determine which unit should be the focus of quality improvement efforts, the quality improvement coordinator can use a data analysis tool such as a Pareto chart, which shows the frequency or impact of different factors or causes in descending order, along with a cumulative line that indicates the percentage of the total. A Pareto chart can help identify the most significant issues or opportunities for improvement, based on the 80/20 rule, which states that 80% of the effects come from 20% of the causes.
* Using the data below, a Pareto chart can be created as follows:
Table
Unit
HAI Rate (%)
A
5
B
7
C
12
D
4
* The Pareto chart shows that Unit C has the highest HAI rate (12%), followed by Unit B (7%), Unit A (5%), and Unit D (4%). Thecumulative line shows that Unit C alone accounts for 40% of the total HAI rate, and Units C and B together account for 63.3% of the total HAI rate. Therefore, according to the Pareto principle, the quality improvement coordinator should focus on Unit C, as it represents the most significant problem area and the greatest opportunity for improvement.
* The quality improvement coordinator can then conduct a root cause analysis to identify the possible factors or causes that contribute to the high HAI rate in Unit C, such as staff compliance, infection control practices, patient characteristics, environmental factors, etc. A root cause analysis can be facilitated by using a visual tool such as a fishbone diagram, which organizes possible factors into categories, such as people, process, equipment, environment, etc. The quality improvement coordinator can also collect and compare data from other units or sources to identify gaps and best practices.
* Based on the root cause analysis, the quality improvement coordinator can then develop and implement an action plan to address the identified causes and improve the HAI rate in Unit C. The action plan should include specific, measurable, achievable, relevant, and time-bound (SMART) goals, interventions, and indicators. The quality improvement coordinator can also involve the staff and leaders of Unit C in the planning and implementation process, to ensure their engagement and ownership of the improvement efforts.
* The quality improvement coordinator should also monitor and evaluate the progress and outcomes of the action plan, using data collection and analysis tools such as run charts, control charts, or statistical process control (SPC), which can show the variation and trends in the HAI rate over time. The quality improvement coordinator should also provide feedback and recognition to the staff and leaders of Unit C, and make adjustments to the action plan as needed, based on the data and evidence.
References:
NAHQ HQ Principles, Module 2: Data Management, Lesson 2.3: Data Analysis Tools, Topic 2.3.1: Pareto Chart, Topic 2.3.2: Fishbone Diagram NAHQ Learning Lab: The Role of the Healthcare Quality Professional in Population Health Management, Module 3: Data Collection and Analysis, Slide 16: Pareto Chart, Slide 18: Fishbone Diagram NAHQ Journal for Healthcare Quality, Volume 42, Issue 5, September/October 2020, Article: Utilization of Improvement Methodologies by Healthcare Quality Professionals During the COVID-19 Pandemic, Page
283: Figure 1. Pareto Chart of COVID-19 Cases by State as of June 30, 2020 NAHQ News and Media, News: Shaping the Future of the Healthcare Quality Profession, Paragraph 5: The Role of the Quality Improvement Coordinator NAHQ Resources, Healthcare Quality Solutions: Ready Your Workforce for Quality, Page 5: The Role of the Quality Improvement Coordinator
NEW QUESTION # 587
......
The 21 century is the information century. Information and cyber technology represents advanced productivity, and its rapid development and wide application have given a strong impetus to economic and social development and the progress of human civilization (CPHQ exam materials). They are also transforming people's lives and the mode of operation of human society in a profound way. So you really should not be limited to traditional paper-based CPHQ Test Torrent in the 21 country especially when you are preparing for an exam, our company can provide the best electronic CPHQ exam torrent for you in this website.
CPHQ Latest Test Discount: https://www.pdf4test.com/CPHQ-dump-torrent.html
P.S. Free 2026 NAHQ CPHQ dumps are available on Google Drive shared by PDF4Test: https://drive.google.com/open?id=1V6vxev8e7BTsnM5aHfi8jyTz3TcBSHAy