P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by DumpTorrent: https://drive.google.com/open?id=1eEYD-qregQDaNg7KKJEkNqmdTnf9nmKY
If you are not satisfied with the function of PDF version which just only provide you the questions and answers, the APP version of EFM exam cram materials can offer you more. APP version can not only simulate the real test scene but also point out your mistakes and notice you to practice many times. This version of NCC EFM Exam Cram materials is rather powerful. If you are willing, you can mark your performance every day and adjust your studying and preparation relatively. EFM exam cram materials will try our best to satisfy your demand.
| Section | Weight | Objectives |
|---|---|---|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
Especially for those students who are headaches when reading a book, EFM study tool is their gospel. Because doing exercises will make it easier for one person to concentrate, and at the same time, in the process of conducting a mock examination to test yourself, seeing the improvement of yourself will makes you feel very fulfilled and have a stronger interest in learning. EFM Guide Torrent makes your learning process not boring at all.
NEW QUESTION # 39
A woman in active labor at 8 cm experiences spontaneous rupture of membranes and acute bright red vaginal bleeding. The uterus is soft and nontender to palpation. The fetal monitor tracing has been normal and now shows tachycardia followed by bradycardia with minimal variability. The maternal blood pressure is 130/76 mm Hg, and the pulse is 86 beats per minute. The most likely cause of these findings is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When bright red vaginal bleeding occurs at the moment of membrane rupture, accompanied by an acute, severe fetal heart rate deterioration, NCC sources emphasize considering conditions causing fetal hemorrhage rather than maternal instability.
The key features in this scenario:
* Timing:Bleeding occurs immediately with spontaneous rupture of membranes-this is classic for vasa previa rupture, where fetal vessels traverse membranes and are torn when the membranes rupture.
* Bleeding characteristics:Bleeding is acute, bright red, and sudden.In vasa previa, the blood observed vaginally is fetal blood, not maternal blood.
* Uterine exam:The uterus is soft and nontender, which strongly argues against abruptio placenta, where the uterus is typically firm, rigid, or painful.
* Maternal vital signs:Maternal blood pressure and pulse are normal, indicating no maternal hypovolemia.In placental abruption or placenta previa with significant maternal bleeding, maternal vitals are often abnormal.Here, the mother is stable, meaning the blood is not maternal-supporting fetal vessel rupture.
* Fetal heart rate pattern:
* Initial tachycardia, followed by
* Bradycardia with minimal variabilitySuch a pattern is consistent with acute fetal blood loss, which rapidly leads to fetal hypovolemia and hypoxia.
* Differential based on NCC-aligned physiology:
A). Abruptio placenta - NOT supported
Typically presents with:
* Painful bleeding
* Firm, tender uterus
* Maternal tachycardia
* Uterine irritabilityNone of these are present.
B). Placenta previa - NOT supported
Classically painless bright red bleeding before or early in labor, not triggered by membrane rupture.
Fetal compromise is less sudden unless maternal shock occurs, which is not the case here.
C). Ruptured vasa previa - CORRECT
Defined by:
* Painless, sudden bright red bleeding at ROM
* Normal maternal vital signs
* Rapid fetal deterioration (tachycardia # bradycardia # minimal variability)
* Soft, nontender uterusThis fits the scenario exactly.
Therefore, the most likely cause is ruptured vasa previa, a recognized obstetric emergency described across AWHONN, NCC C-EFM references, and maternal-fetal physiology texts such as Menihan and Creasy & Resnik.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 40
The factor that differentiates a prolonged deceleration from bradycardia is:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NICHD/NCC definitions:
* Prolonged deceleration: decrease in FHR #15 bpm lasting 2 to 10 minutes
* Bradycardia: baseline FHR <110 bpm lasting #10 minutes
The differentiating factor is duration, not rate and not contraction relationship.
* Before 10 minutes # prolonged deceleration
* At or beyond 10 minutes # new baseline # bradycardia
Thus, the factor that differentiates the two is length of time it lasts.
References:NICHD FHR Definitions; NCC C-EFM Candidate Guide; AWHONN; Miller; Menihan.
NEW QUESTION # 41
Maternal conditions of autoimmunity can result in fetal heart block due to antibodies that target:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC physiology content specifically includes maternal autoimmune influences on fetal cardiac conduction.
Conditions such as maternal lupus (SLE) or Sjogren's syndrome may produce anti-Ro/SSA and anti-La
/SSB antibodies. These antibodies cross the placenta and damage fetal conduction tissue.
The primary site of injury is the fetal atrioventricular (AV) node, leading to:
* First-, second-, or complete third-degree heart block
* A slow, regular ventricular rate typically 50-70 bpm
* Loss of beat-to-beat variability because ventricular myocardium does not display normal autonomic modulation This mechanism is extensively described in AWHONN, NCC physiology materials, and maternal-fetal physiology texts.
Option A: Antibodies do not target fetal RBCs; that describes hemolytic disease of the newborn.
Option B: Targeting maternal WBCs is not fetal-specific.
The correct affected structure is the fetal AV node.
Therefore, the correct answer is C. The fetal atrioventricular node.
References:NCC C-EFM Candidate Guide (2025); NCC Physiology Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 42
This tracing has lasted for 20 minutes in a woman who is 6 cm dilated. The most appropriate intervention is: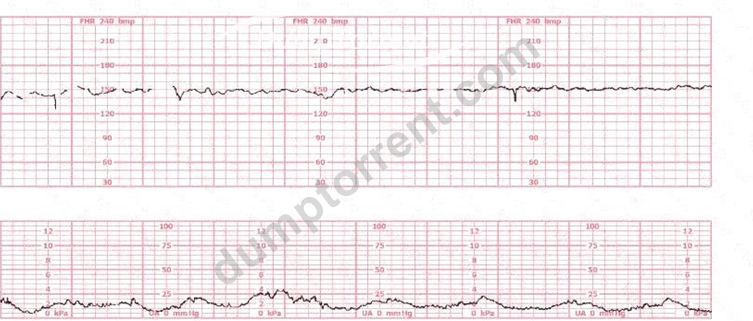
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline approximately 135-140 bpm
* Minimal variability
* No accelerations
* No recurrent decelerations
* Category II for 20 minutes
According to NCC, AWHONN, and NICHD, minimal variability persisting # 20 minutes without accelerations requires assessment of fetal acid-base status, and fetal scalp stimulation is an accepted method to evaluate fetal well-being when a Category II tracing persists.
Fetal scalp stimulation:
* Should produce an acceleration # 15 bpm lasting # 15 seconds
* A positive response indicates intact fetal nervous system and normal pH
* If no acceleration occurs # further intrauterine resuscitation or expedited delivery may be required Why other options are incorrect:
* A. Delivery - Not indicated; this is Category II, not Category III.
* C. IV bolus - IV hydration may improve variability, but assessment of fetal status comes first after
20 minutes of minimal variability.
Thus, the correct answer is B. Fetal scalp stimulation.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; NICHD Three-Tier System; Menihan; Miller's Pocket Guide; Simpson & Creehan.
NEW QUESTION # 43
The baseline fetal heart rate in this tracing is: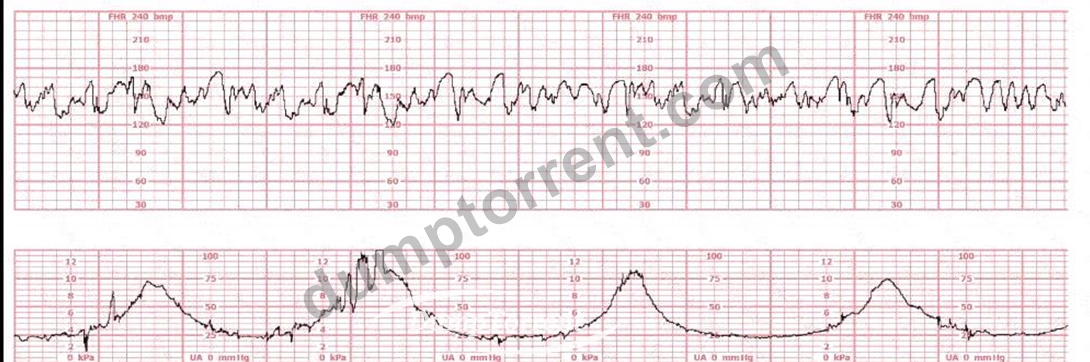
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
On the tracing:
* FHR consistently ranges 170-185 bpm.
* Variability remains present, confirming adequate signal.
* This pattern persists for the required minimum 10-minute baseline window.
NICHD/NCC define fetal tachycardia as:
* Baseline > 160 bpm for at least 10 minutes
Because the FHR is well above 160 for the whole reviewable period, the baseline is tachycardic.
Why the other answers are incorrect:
* A. 155 bpm - Too low; FHR visually averages well above this.
* B. Indeterminate - Not applicable; variability is clear and the tracing meets the #10-minute rule.
Correct answer: C. Tachycardia
References:NICHD Definitions; NCC C-EFM Candidate Guide; AWHONN; Miller; Menihan.
NEW QUESTION # 44
......
Download the free EFM pdf demo file of DumpTorrent brain dumps. Checking the worth of the EFM exam questions and learns the format of questions and answers. A few moments are enough to introduce you to the excellent of the EFM Brain Dumps and the authenticity and relevance of the information contained in them.
EFM Valid Braindumps Ebook: https://www.dumptorrent.com/EFM-braindumps-torrent.html
DOWNLOAD the newest DumpTorrent EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1eEYD-qregQDaNg7KKJEkNqmdTnf9nmKY