BTW, DOWNLOAD part of PassSureExam EFM dumps from Cloud Storage: https://drive.google.com/open?id=1ZiyjcxMtmSEIt00k1APErj4QOoAhxSIA
Taking practice tests is particularly helpful for those who have exam anxiety. Our practice tests are user-friendly and customizable. Windows support the desktop practice test software. Our web-based practice test is compatible with all browsers and operating systems. The web-based Certified - Electronic Fetal Monitoring (EFM) practice test is similar to the desktop-based exam and can be taken on any browser without needing to download separate software.
| Section | Objectives |
|---|---|
| Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Fetal Heart Rate Interpretation | - Accelerations and decelerations - Category I, II, and III tracing interpretation - Baseline rate and variability |
| Intrapartum Assessment and Monitoring | - Risk assessment during labor - External and internal monitoring techniques |
| Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
>> EFM Latest Braindumps Ppt <<
Passing the NCC EFM certification exam is necessary for professional development, and employing real EFM Exam Dumps can assist applicants in reaching their professional goals. These actual EFM questions assist students in discovering areas in which they need improvement, boost confidence, and lower anxiety. Candidates will breeze through Certified - Electronic Fetal Monitoring (EFM) certification examination with flying colors and advance to the next level of their jobs if they prepare with updated EFM exam questions.
NEW QUESTION # 27
Interventions to decrease uterine activity should take place:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Tachysystole = >5 contractions in 10 minutes averaged over 30 minutes (NICHD).
However, NCC and AWHONN intervention guidelines state:
* If tachysystole appears in one or two consecutive 10-minute segments, especially with Category II or III patterns, intervention must begin immediately.
* Intervention includes:
* Stopping/reducing oxytocin
* Maternal repositioning
* IV bolus
* Tocolysis if needed
Why the wrong answers are wrong:
* A. Waiting 30 minutes delays necessary fetal resuscitation.
* C. Stage of labor does not determine when to intervene.
Correct answer: B. If tachysystole is seen for one or two 10-minute segments References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan.
NEW QUESTION # 28
When the fetal heart rate is measured by a Doppler transducer and the intervals between heart beats are persistently identical, this shows as
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Variability is created by beat-to-beat differences in fetal cardiac intervals due to autonomic nervous system modulation. AWHONN specifies that absent variability appears as "a near-straight line with minimal or no discernible oscillations," which occurs when all beat intervals are identical.
Menihan notes that Doppler displays variability based on mechanical motion and will show flat, unchanging intervals when fetal autonomic modulation is suppressed, reflecting absent variability.
Bradycardia refers to a baseline <110 bpm and does not describe the uniformity of intervals. A normal baseline may still show variability; it cannot have identical beat-to-beat intervals, as this violates the definition of variability in NICHD terminology.
Simpson & Creehan state that absent variability is a significant marker of impaired fetal oxygenation or CNS depression.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 29
The main reason intrauterine pressure catheters are placed is to:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Intrauterine pressure catheters (IUPCs) are an internal uterine activity monitoring device used when external tocodynamometry does not provide adequate assessment of contraction strength or frequency.
According to NCC, AWHONN, Miller, and Menihan, the primary indication for placing an IUPC is to obtain accurate, quantitative measurement of uterine activity.
Purpose of IUPC (per NCC and AWHONN):
* Measures exact intrauterine pressure in mmHg
* Calculates Montevideo units (MVUs) to evaluate adequacy of labor
* Clearly differentiates:
* Frequency
* Duration
* Strength (intensity)
* Resting tone
NCC explicitly lists the primary purpose as:
"Accurate assessment of uterine contraction pattern and intensity."
Why the other options are incorrect:
A). Define the quality of the fetal baseline - Incorrect
* Fetal heart rate (FHR) baseline quality is determined by fetal ECG or FSE, not IUPC.
* IUPCs monitor the uterus, not the fetal cardiac signal.
C). Rule out artifact - Incorrect
* While an IUPC can reduce artifact from the toco, this is not its primary purpose.
* Artifact is more commonly an issue with external FHR monitoring, corrected by repositioning or placing a fetal scalp electrode-not by using an IUPC.
B). Determine the contraction pattern
This aligns directly with NCC's Electronic Monitoring Equipment domain: IUPCs provide the most accurate and reliable measurement of uterine activity when external monitoring is inadequate.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 30
The fetal heart rate tracing shown represents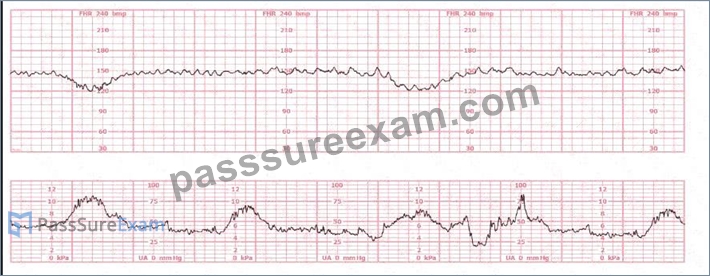
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The tracing demonstrates a baseline within normal limits, moderate variability, and recurrent variable decelerations associated with contractions. According to NICHD/NCC definitions reproduced in AWHONN' s Fetal Heart Monitoring Principles & Practices and Menihan's Electronic Fetal Monitoring, recurrent variable decelerations with preserved variability classify the tracing as Category II.
A Category I pattern must show baseline 110-160, moderate variability, and absence of late or variable decelerations. Because this tracing shows recurrent variable decelerations, it does not meet Category I criteria.
Category III requires absent variability PLUS recurrent late decelerations, recurrent variable decelerations, bradycardia, or a sinusoidal pattern. This tracing shows moderate variability, therefore it cannot be Category III.
Simpson & Creehan emphasize that variable decelerations reflect cord compression and fall into Category II unless accompanied by absent variability. Miller's Pocket Guide confirms that moderate variability maintains fetal compensatory reserve, keeping the pattern in Category II.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 31
A woman is admitted at 41-weeks gestation for fetal evaluation following a motor vehicle accident. She reports that she hit her abdomen on the steering wheel. The underlying physiology of the tracing is most likely: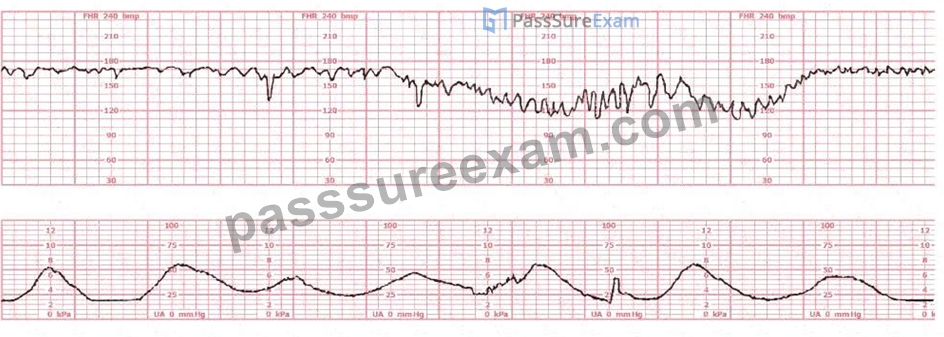
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing shows recurrent late decelerations, decreased variability, and subtle baseline shifts-findings that strongly correspond to uteroplacental insufficiency. In trauma cases, NCC emphasizes that placental abruption is the most common fetal complication, caused by shearing forces separating the placenta from the uterine wall.
Key physiologic points per NCC/AWHONN/Menihan:
* Maternal blunt abdominal trauma frequently leads to partial or concealed abruption.
* Abruption produces decreased uteroplacental blood flow, resulting in:
* Late decelerations
* Minimal/absent variability
* Baseline shifts or instability
Cord accident (option A) typically produces variable decelerations, not late-pattern decelerations.
Fetal trauma (option B) is extremely rare and does not produce a consistent deceleration pattern.
Thus, the physiology most consistent with this tracing and mechanism of injury is placental abruption.
References:NCC C-EFM Candidate Guide (2025); NCC Physiology Domain; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 32
......
We are all well aware that a major problem in the industry is that there is a lack of quality study materials. Our EFM braindumps provides you everything you will need to take a certification examination. Details are researched and produced by EFM Dumps Experts who are constantly using industry experience to produce precise, logical verify for the test. You may get EFM exam dumps from different web sites or books, but logic is the key.
EFM Certification Dump: https://www.passsureexam.com/EFM-pass4sure-exam-dumps.html
BONUS!!! Download part of PassSureExam EFM dumps for free: https://drive.google.com/open?id=1ZiyjcxMtmSEIt00k1APErj4QOoAhxSIA