さらに、PassTest EFMダンプの一部が現在無料で提供されています:https://drive.google.com/open?id=1By3F9aCBp2eZKBxo2VHIRjYa952wPO0P
NCCのEFMの試験の資料やほかのトレーニング資料を提供しているサイトがたくさんありますが、NCCのEFMの認証試験の高品質の資料を提供しているユニークなサイトはPassTestです。PassTestのガイダンスとヘルプを通して、初めにNCCのEFM「Certified - Electronic Fetal Monitoring」の認証を受けるあなたは、気楽に試験に合格すことができます。PassTestが提供した問題と解答は現代の活力がみなぎる情報技術専門家が豊富な知識と実践経験を活かして研究した成果で、あなたが将来IT分野でより高いレベルに達することに助けを差し上げます。
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Topic 2: Physiology | 11% | - Maternal-Fetal Physiology
|
| Topic 3: Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Topic 4: Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
| Topic 5: Professional Issues | 5% | - Clinical Practice and Safety
|
当社のEFMテストトレントは、チャレンジに取り組み、EFM試験に合格するのに役立つ新しい方法を探し続けています。そして、EFM認定テストは長い間集中しており、教材の設計で大量のリソースと経験を蓄積してきました。あなたが楽しみにしているEFM試験の証明書を取得するのを助けるために、熟練した意欲的なスタッフがたくさんいます。私たちはプロのチームとEFM学習ツールを信頼しており、心から信頼してください。
質問 # 43
A fetus displays a baseline heart rate of 125 beats per minute with moderate variability. During a contraction, the baseline rate drops abruptly to 80 beats per minute with gradual return to baseline over 90 seconds. This is classified as:
正解:B
解説:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NICHD definitions:
A variable deceleration is identified by:
* Abrupt onset(drop from baseline to nadir in <30 seconds)
* Depth #15 bpm
* Duration #15 seconds and <2 minutes
* Variable timing relative to contractions
* Variable shape (sharp drop, jagged descents, rapid recovery)
The scenario describes:
* Abrupt drop from 125 # 80 bpm (rapid onset)
* Lasting 90 seconds (still <2 minutes)
* Gradual return but still within variable range
* Occurring during a contraction
* Depth >15 bpm
This meets ALL criteria for a variable deceleration.
Why the other options are wrong:
* A. Early deceleration
* Requires gradual onset (>30 seconds).
* Mirrors contraction shape.
* Caused by head compression.
* This decel is abrupt, so NOT early.
* B. Prolonged deceleration
* Requires #2 minutes and <10 minutes.
* This decel lasts 90 seconds, which is below the threshold.
Correct classification: Variable deceleration.
References:NICHD FHR Definitions; NCC Pattern Recognition Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
質問 # 44
This tracing has lasted for 20 minutes in a woman who is 6 cm dilated. The most appropriate intervention is: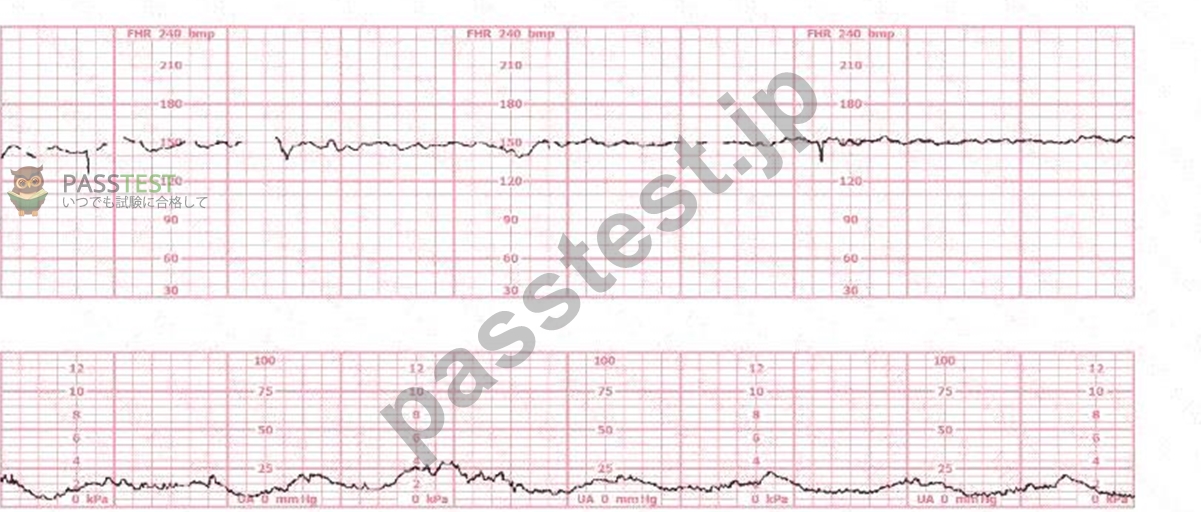
正解:A
解説:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline approximately 135-140 bpm
* Minimal variability
* No accelerations
* No recurrent decelerations
* Category II for 20 minutes
According to NCC, AWHONN, and NICHD, minimal variability persisting # 20 minutes without accelerations requires assessment of fetal acid-base status, and fetal scalp stimulation is an accepted method to evaluate fetal well-being when a Category II tracing persists.
Fetal scalp stimulation:
* Should produce an acceleration # 15 bpm lasting # 15 seconds
* A positive response indicates intact fetal nervous system and normal pH
* If no acceleration occurs # further intrauterine resuscitation or expedited delivery may be required Why other options are incorrect:
* A. Delivery - Not indicated; this is Category II, not Category III.
* C. IV bolus - IV hydration may improve variability, but assessment of fetal status comes first after
20 minutes of minimal variability.
Thus, the correct answer is B. Fetal scalp stimulation.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; NICHD Three-Tier System; Menihan; Miller's Pocket Guide; Simpson & Creehan.
質問 # 45
When fetal arterial blood pressure increases, the baroreceptors send impulses to the vagus nerve resulting in:
正解:B
解説:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Fetal baroreceptors, located primarily in the carotid sinus and aortic arch, respond to increases in fetal arterial pressure. When activated, they stimulate the vagus nerve, causing:
* Reflex parasympathetic activation
* Decreased FHR (vagal slowing)
This is a well-established physiologic mechanism referenced throughout NCC's physiology domain. NCC emphasizes that variable decelerations, especially short deep drops, can occur when transient increases in fetal blood pressure from cord compression activate these baroreceptors.
Option B, decreased PO#, relates to chemoreceptor-mediated responses-not baroreceptors.
Option C, reflex tachycardia, is mediated by sympathetic activation and occurs when BP falls, not rises.
Thus, the correct physiologic response is A. Decreased heart rate.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline (Physiology Domain); AWHONN Fetal Heart Monitoring; Menihan Electronic Fetal Monitoring; Creasy & Resnik Maternal-Fetal Physiology; Simpson & Creehan Perinatal Nursing.
質問 # 46
What is the appropriate interpretation of this tracing?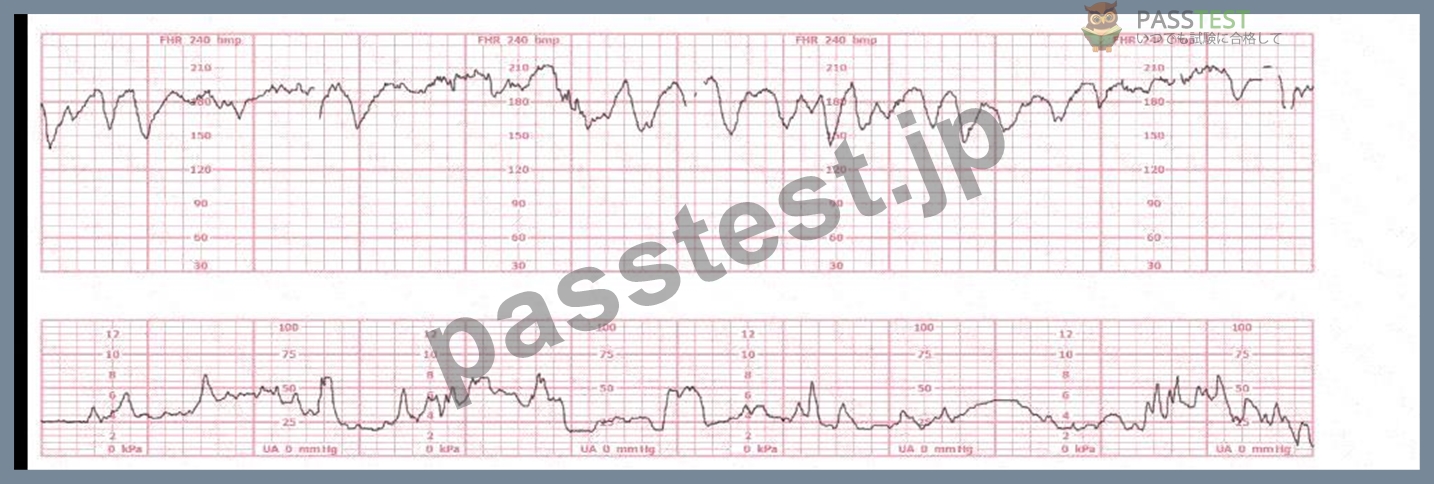
正解:B
解説:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing demonstrates:
* Baseline ~150 bpm
* Variability # 25 bpm amplitude, highly erratic and wide
* No sustained decelerations
* No sustained accelerations # 2 min
NICHD/NCC definition of marked variability:
Amplitude of baseline FHR fluctuations greater than 25 bpm.
Marked variability often reflects transient fetal autonomic instability due to:
* Fetal stimulation
* Mild hypoxemia
* Maternal anxiety
* Drugs (e.g., butorphanol)
Why other answers are incorrect:
* B. Multiple prolonged accelerations - No accelerations of #2 minutes are present.
* C. Tachycardia with variables - Baseline is NOT tachycardic (>160 bpm), and decelerations are not present.
Thus, the correct interpretation is A. Marked variability.
References:NICHD FHR Definitions; NCC C-EFM Candidate Guide; AWHONN; Menihan; Simpson & Creehan.
質問 # 47
A pattern of recurrent variable decelerations would move from Category II to Category III if what fetal heart rate change occurs?
正解:A
解説:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Category III criteria include:
* Absent variability with recurrent variable decelerations
* Absent variability with recurrent lates
* Absent variability with bradycardia
* Sinusoidal pattern
Thus, recurrent variables become Category III when accompanied by absent variability, indicating fetal decompensation.
Why the other answers are wrong:
* B. Late decelerations # Category III only if combined with absent variability.
* C. Tachysystole # Contraction pattern, not a FHR characteristic.
Correct answer: Absent variability.
References:NCC C-EFM Candidate Guide; NICHD Definitions; AWHONN FHMPP.
質問 # 48
......
PassTestのNCCのEFM試験トレーニング資料は現在で一番人気があるダウンロードのフォーマットを提供します。PDFとソフトのフォーマットで、ダウンロードするのは易いです。PassTestが提供した製品がIT専門家は実際の経験を活かして作った最も良い製品で、あなたが自分の目標を達成するようにずっと一生懸命頑張っています。
EFM模擬モード: https://www.passtest.jp/NCC/EFM-shiken.html
ちなみに、PassTest EFMの一部をクラウドストレージからダウンロードできます:https://drive.google.com/open?id=1By3F9aCBp2eZKBxo2VHIRjYa952wPO0P