DOWNLOAD the newest VCEEngine MCCQE PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=16iICp40KXqQtFvh6hAomaus7lfsBA-qm
After you really improve your strength, you will find that your strength can bring you many benefits. Users of our MCCQE practice prep can prove this to you. You have to believe that your strength matches the opportunities you have gained. And the opportunities you get are the basic prerequisite for your promotion and salary increase. After you use our MCCQE Exam Materials, you will more agree with this. With the help of our MCCQE study guide, nothing is impossible to you.
| Section | Weight | Objectives |
|---|---|---|
| Dimensions of Care | 50% | - Health Promotion and Illness Prevention - Acute Care - Chronic Care - Assessment and Diagnosis |
| Physician Activities | 50% | - Management - Psychosocial Aspects - Communication - Professional Behaviours |
>> MCCQE Valid Test Materials <<
In order to let you understand our products in detail, our MCCQE Part 1 Exam test torrent has a free trail service for all customers. You can download the trail version of our MCCQE study torrent before you buy our products, you will develop a better understanding of our products by the trail version. In addition, the buying process of our MCCQE exam prep is very convenient and significant. You will receive the email from our company in 5 to 10 minutes after you pay successfully; you just need to click on the link and log in, then you can start to use our MCCQE study torrent for studying. Immediate download after pay successfully is a main virtue of our MCCQE Part 1 Exam test torrent. At the same time, you will have the chance to enjoy the 24-hours online service if you purchase our products, so we can make sure that we will provide you with an attentive service.
NEW QUESTION # 42
A 4-month-old girl is brought by a parent to your clinic with a history of recurrent vomiting since birth. She cries with feeding and has not gained weight in the last 2 weeks. Her hemoglobin level is 95 g/L (100-125).
The patient is currently being fed thickened hypoallergenic formula. Which one of the following is the most appropriate therapy?
Answer: E
Explanation:
This infant has persistent vomiting with feeding-associated distress and poor weight gain, despite appropriate initial nonpharmacologic measures (thickened feeds and hypoallergenic formula). MCCQE pediatrics objectives emphasize distinguishing physiologic reflux ("happy spitter") from gastroesophageal reflux disease (GERD), which is suggested by feeding aversion/crying and failure to thrive. When conservative strategies fail and GERD is causing significant symptoms or complications (e.g., poor growth, suspected esophagitis contributing to irritability and possibly anemia), escalation to acid suppression is appropriate; a proton pump inhibitor such as omeprazole is used to treat acid-related esophageal injury and improve symptoms in selected infants with suspected erosive disease.
Metoclopramide is not preferred due to limited benefit and risk of extrapyramidal adverse effects. Calcium carbonate antacids are not recommended as ongoing therapy in infants due to safety concerns and inferior efficacy for esophagitis. Bismuth sulfate is not indicated. Loperamide is inappropriate and potentially harmful in infants. Continued monitoring of growth and reassessment for alternative diagnoses or alarm features is essential.
NEW QUESTION # 43
A 30-year-old woman presents to the office with her partner and reports that they are planning for her to conceive soon. They visited Mexico recently and are concerned about exposure to the Zika virus. Which one of the following is the best next step?
Answer: C
Explanation:
Comprehensive and Detailed Explanation:
The Zika virus can be sexually transmitted and poses a serious risk of congenital Zika syndrome if infection occurs during pregnancy. The CDC and WHO recommend that couples delay conception for at least 3 months after potential male exposure due to the virus's persistence in semen.
Toronto Notes 2023 - Infectious Diseases / Travel Medicine:
"Zika virus may persist in semen for weeks. Couples should delay conception for 3 months after male exposure, even if asymptomatic." MCCQE1 Objectives (Public Health > 65-3: Travel Medicine and Reproductive Health):
"Candidates must counsel appropriately regarding risks of Zika in conception and apply current public health recommendations." Testing (B) is not reliable for asymptomatic individuals. Antivirals (E) are ineffective. Condoms (D) do reduce risk. Specialist referral (A) is not needed in most cases with no complications.
-
NEW QUESTION # 44
A 25-year-old nulligravida woman presents after trying to conceive for 2 years without success. She is healthy, with regular menstrual periods. She denies any unusual hair growth, weight changes, or breast discharge. She gets occasional outbreaks of acne. Blood work done with her next menstrual period produces the following results:
Follicle-stimulating hormone, follicular phase: 6.2 U/L (5.0-20.0) on day 3 of menstrual cycle Luteinizing hormone, follicular phase: 6 U/L (5-22) on day 3 of menstrual cycle Estradiol: 163 pmol/L (50-200) on day 15 of menstrual cycle Thyrotropin (thyroid-stimulating hormone): 2.5 mU/L (0.4-5.0) Prolactin: 40 µg/L (4-30) Given the results of her blood work, which one of the following is the best next step?
Answer: C
Explanation:
This patient meets the definition of infertility (no conception after 12 months; here 2 years). Her day-3 FSH
/LH and mid-cycle estradiol are within expected ranges, and TSH is normal, making thyroid disease unlikely.
The key abnormality is elevated prolactin (40 µg/L) . MCCQE objectives emphasize identifying reversible endocrine causes of infertility: hyperprolactinemia can impair fertility by disrupting hypothalamic GnRH pulsatility and ovulatory function, and treatment improves pregnancy rates. The appropriate next management is a dopamine agonist (e.g., bromocriptine) to lower prolactin and restore normal reproductive axis function.
Pituitary MRI is generally reserved for marked or persistent elevations suggestive of prolactinoma (often much higher levels) or when there are neurologic symptoms (e.g., headaches, visual field defects). IVF is not first-line when a treatable endocrine abnormality is present. Mammography is unrelated to mild hyperprolactinemia without breast findings. Treating the elevated prolactin addresses a likely contributor before proceeding to more invasive fertility interventions.
NEW QUESTION # 45
An 80-year-old woman presents to the Emergency Department with dizziness. She has a medical history of coronary artery disease. On examination, she is alert and oriented. Her vital signs are as follows:
Her electrocardiogram is shown in the image.
Which one of the following is the most likely diagnosis?
Blood pressure
80/60 mm Hg
Heart rate
40/min
Respiratory rate
12/min
Her electrocardiogram is shown in the attached image. Which one of the following is the most likely diagnosis?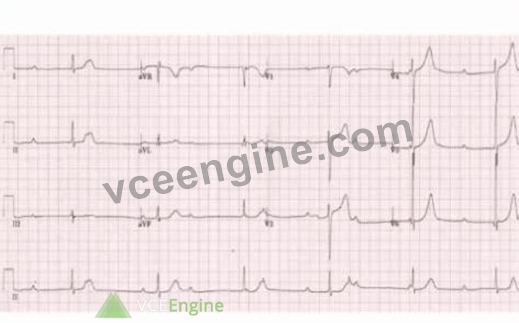
Answer: E
Explanation:
Comprehensive and Detailed Explanation:
The ECG reveals:
Regular P waves that are not consistently followed by QRS complexes
A dissociation between the atrial (P wave) and ventricular (QRS complex) activity A slow ventricular rate (~40 bpm) independent of atrial rate These findings are characteristic of a third-degree (complete) atrioventricular (AV) block, where there is no conduction of atrial impulses to the ventricles. The atria and ventricles beat independently, and the ventricular rate is maintained by an escape rhythm, often junctional or ventricular in origin.
This correlates with the patient's symptoms (dizziness, hypotension) and bradycardia, suggesting inadequate cardiac output due to AV dissociation.
Toronto Notes 2023 - Cardiology:
"Third-degree AV block shows complete AV dissociation with independent atrial and ventricular activity. It typically presents with bradycardia and hypotension. Urgent pacing may be required." MCCQE1 Objectives (Cardiology > 34-2: Bradyarrhythmias and Conduction Disorders):
"Candidates must identify complete heart block and recognize its clinical urgency." Ruling out other options:
A). Sinus bradycardia would show regular P waves with 1:1 P-QRS conduction.
B). First-degree AV block has prolonged PR intervals ( > 200 ms) but all P waves are conducted.
D). Junctional escape rhythm may present with bradycardia, but P waves would be absent, inverted, or occur after QRS complexes.
E). Mobitz type I (Wenckebach) has progressively lengthening PR intervals before a dropped QRS.
NEW QUESTION # 46
A 48-year-old woman presents with a 2-year history of regular, heavy menstrual flow. She has a BMI of 54, poorly controlled type 2 diabetes, and obstructive sleep apnea. Laboratory results are as follows:
Hemoglobin: 82 g/L (123-157)
Ferritin: 6 µg/L (11-307)
Endometrial biopsy: Absence of hyperplasia or malignancy
Transvaginal ultrasound:
* Uterus: 12 cm × 8.2 cm × 6 cm
* Intramural fibroids
* Endometrial thickness: 14 mm
* Ovaries: Normal
Which one of the following is the best next step?
Answer: D
Explanation:
The levonorgestrel-releasing intrauterine system (LNG-IUS) is the first-line treatment for heavy menstrual bleeding, particularly in women with risk factors for endometrial hyperplasia and contraindications to systemic hormones (e.g., morbid obesity, diabetes, OSA).
Toronto Notes 2023 - Gynecology, "Abnormal Uterine Bleeding" Section:
"The LNG-IUS is highly effective in reducing menstrual bleeding and improving hemoglobin levels. It is particularly recommended in women with obesity, chronic anovulation, or contraindications to estrogen." MCCQE1 Objectives (Obstetrics and Gynecology > 82-1: Abnormal Uterine Bleeding):
"Candidates must consider the LNG-IUS as a preferred non-surgical treatment for chronic heavy menstrual bleeding when endometrial pathology has been excluded." Oral contraceptives (C) are not first-line in morbid obesity due to increased thromboembolic risk. Cyclic medroxyprogesterone (D) is less effective than LNG-IUS. Hysterectomy (A) is definitive but should follow failure of conservative therapy.
NEW QUESTION # 47
......
We will provide 24-hour online service for you on our MCCQE exam questios. If you can’t decide what kind of MCCQE exam practice to choose, you shall have a chance to consult us, You can ask the questions that you want to know about our MCCQE Study Guide, we will listen to you carefully, according to your MCCQE exam, we guarantee to meet your requirements without wasting your purchasing funds.
MCCQE Exam Details: https://www.vceengine.com/MCCQE-vce-test-engine.html
2026 Latest VCEEngine MCCQE PDF Dumps and MCCQE Exam Engine Free Share: https://drive.google.com/open?id=16iICp40KXqQtFvh6hAomaus7lfsBA-qm