그리고 ITDumpsKR EFM 시험 문제집의 전체 버전을 클라우드 저장소에서 다운로드할 수 있습니다: https://drive.google.com/open?id=1kxJ9BAHWnZjE5KsVbE-mN6jKrx8WnYrG
Pass4Tes가 제공하는 제품을 사용함으로 여러분은 IT업계하이클래스와 멀지 않았습니다. Pass4Tes 가 제공하는 인증시험덤프는 여러분을NCC인증EFM시험을 안전하게 통과는 물론 관연전업지식장악에도 많은 도움이 되며 또한 우리는 일년무료 업뎃서비스를 제공합니다.
| Section | Objectives |
|---|---|
| Topic 1: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Topic 2: Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Topic 3: Fetal Heart Rate Interpretation | - Baseline rate and variability - Accelerations and decelerations - Category I, II, and III tracing interpretation |
| Topic 4: Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
| Topic 5: Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Topic 6: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
현재 많은 IT인사들이 같은 생각하고 잇습니다. 그것은 바로NCC EFM인증시험자격증 취득으로 하여 IT업계의 아주 중요한 한걸음이라고 말입니다.그만큼NCC EFM인증시험의 인기는 말 그대로 하늘을 찌르고 잇습니다,
질문 # 78
The black pattern represents the heart rate pattern for Baby A. The blue pattern represents the heart rate pattern for Baby B. A possible etiology of the baseline fetal heart rate of Baby A is: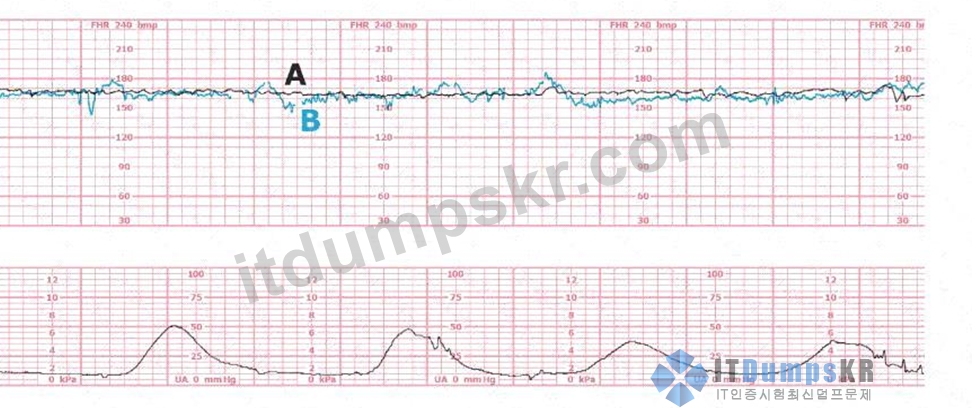
정답:C
설명:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The black tracing (Baby A) demonstrates:
* Baseline ~170-175 bpm
* Moderate variability
* No recurrent decelerations
This is fetal tachycardia.
NCC physiology guidelines list common causes of fetal tachycardia:
* Maternal fever / infection (chorioamnionitis)
* Maternal dehydration
* Maternal anxiety
* Maternal hyperthyroidism
* Fetal infection
* Certain medications (terbutaline, illicit stimulants)
Why the other options are incorrect:
* A. Fetal positioning does not influence baseline heart rate.
* C. Magnesium sulfate typically lowers fetal baseline and variability-it does not cause tachycardia.
Thus, the most likely etiology is infection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan EFM; Simpson & Creehan; Creasy & Resnik.
질문 # 79
A woman has been 5 cm dilated for the past 3 hours. The tracing shown has developed over the last 30 minutes. The best initial course of action is to: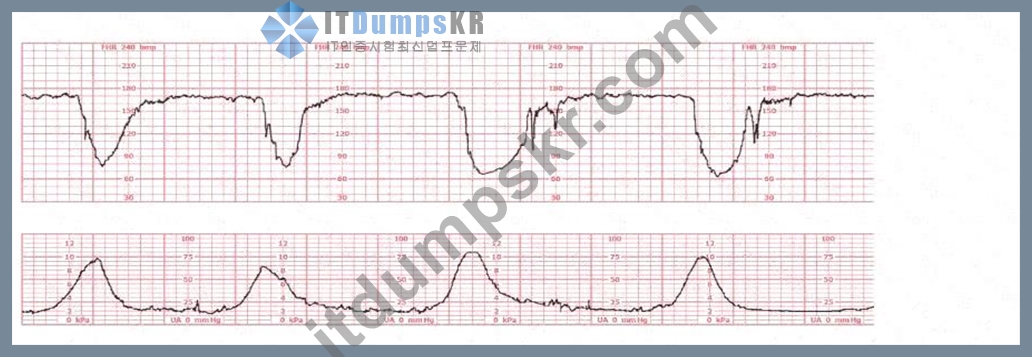
정답:A
설명:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The fetal heart rate tracing demonstrates recurrent deep variable decelerations with a rapid drop in FHR, a V-shaped pattern, and slow return to baseline. These are classic signs of cord compression. According to NCC, AWHONN, Miller, Menihan, and Simpson, recurrent variable decelerations require immediate intrauterine resuscitative interventions before any decision regarding operative birth.
NCC-aligned intervention steps include:
* Maternal repositioning (first-line for cord compression)
* Reducing or stopping oxytocin if infusing
* IV fluid bolus
* Amnioinfusion (if appropriate and recurrent deep variables persist)
* Oxygen only if other measures fail (per NCC/AWHONN updated guidance)
The cervix has remained unchanged at 5 cm for 3 hours (a prolonged latent or early active labor pattern), but the fetal tracing shows Category II-recurrent variable decelerations. Category II dictates corrective action, not immediate delivery unless it progresses to Category III.
Cesarean birth (option C) is reserved for:
* Persistent Category III
* Failure of intrauterine resuscitation
* Proven fetal intoleranceNone of these conditions have been met yet.
Thus, the correct initial management is B. Perform intrauterine resuscitative measures.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD FHR Definitions; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
질문 # 80
Maternal fever can cause fetal tachycardia because the increased maternal temperature:
정답:C
설명:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Maternal hyperthermia-most commonly from infection-causes a rise in fetal temperature, which increases fetal metabolic rate. The fetus responds by increasing heart rate to meet the increased oxygen demand.
Effects include:
* Increased fetal oxygen consumption
* Enhanced fetal cardiac output
* Resultant tachycardia, often 160-180 bpm
This mechanism is repeatedly outlined in NCC's physiology domain, AWHONN, Menihan, Simpson, and Creasy & Resnik.
Option A is incorrect because maternal fever does not reduce perfusion.
Option C is incorrect because catecholamines are often elevated, not inhibited.
Thus, the mechanism is increased fetal metabolism.
References:NCC C-EFM Candidate Guide; NCC Physiology Domain; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy
& Resnik Maternal-Fetal Medicine.
질문 # 81
This fetal heart rate tracing is from a woman in the second stage of labor. This tracing is best interpreted as: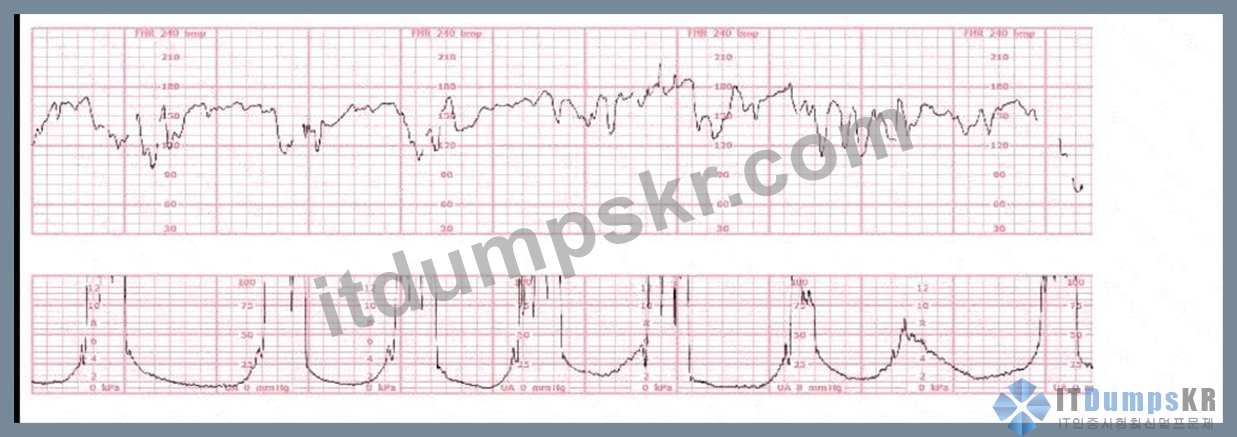
정답:A
설명:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The tracing shows the classic features of variable decelerations:
* Abrupt onset (<30 seconds from baseline to nadir)
* Rapid drop followed by a rapid recovery
* Significant variability in shape, depth, and timing
* "Shouldering"-brief accelerations before or after the deceleration, typical of cord compression
* The decelerations vary in appearance and timing relative to contractions In second stage, this pattern is extremely common due to:
* Recurrent cord compression during descent
* Maternal pushing
* Reduced amniotic fluid with advancing labor
Why the other options are incorrect:
A). Intermittent late decelerations
* Late decelerations are uniform, smooth, begin after the contraction peak, and recover after the contraction ends.
* This tracing shows abrupt, variable-shaped, non-uniform decels # NOT late decels.
C). Wandering baseline
* A wandering baseline is a slowly fluctuating, low-amplitude, smooth, preterminal pattern.
* This tracing shows an identifiable baseline with variability and clear decelerations, not wandering baseline.
Thus, the tracing is most consistent with variable decelerations.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; NICHD FHR Definitions; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
질문 # 82
The fetal heart rate tracing shown is consistent with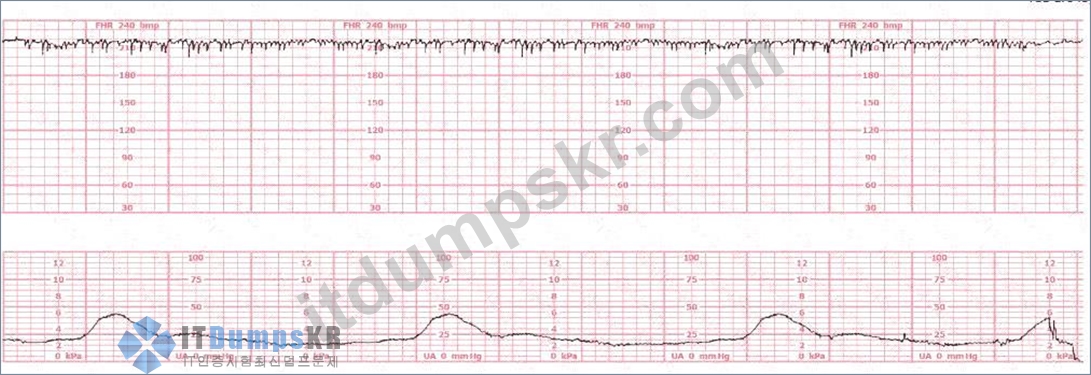
정답:A
설명:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The tracing demonstrates a very rapid, highly regular baseline fetal heart rate with minimal beat-to-beat variability-characteristic of fetal supraventricular tachycardia (SVT). NCC-recommended references, including AWHONN's Fetal Heart Monitoring Principles & Practices, Menihan's Electronic Fetal Monitoring: Concepts and Applications, Simpson & Creehan's Perinatal Nursing, and Creasy & Resnik's Maternal-Fetal Medicine all describe fetal SVT as a sustained tachyarrhythmia usually greater than 200 bpm
, narrow-complex, and extremely regular in appearance.
AWHONN teaches that SVT appears as a "tight, rapid, uniform baseline with minimal variability." Menihan states that "SVT may present on EFM as a nearly straight line due to the rapid, consistent rate with micro- oscillations." This differs significantly from artifact, which appears disorganized, erratic, and inconsistent in amplitude. Additionally, "half-counting" is a Doppler misinterpretation that records half of an extremely fast fetal rate, usually resulting in a falsely lower heart rate-not the very rapid tracing shown here.
Creasy & Resnik emphasize that SVT is the most common pathological fetal arrhythmia and can lead to fetal compromise if prolonged, making accurate recognition essential. Miller's Pocket Guide to Fetal Monitoring also identifies SVT as a pattern with a "smooth, fast rhythm lacking normal variability." All authoritative NCC-recommended references support that this EFM pattern is consistent with fetal SVT, not artifact or half-counting.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide to Fetal Monitoring
질문 # 83
......
우선 우리ITDumpsKR 사이트에서NCC EFM관련자료의 일부 문제와 답 등 샘플을 제공함으로 여러분은 무료로 다운받아 체험해보실 수 있습니다.체험 후 우리의ITDumpsKR에 신뢰감을 느끼게 됩니다. ITDumpsKR에서 제공하는NCC EFM덤프로 시험 준비하시면 편안하게 시험을 패스하실 수 있습니다.
EFM최고품질 덤프문제모음집: https://www.itdumpskr.com/EFM-exam.html
ITDumpsKR EFM 최신 PDF 버전 시험 문제집을 무료로 Google Drive에서 다운로드하세요: https://drive.google.com/open?id=1kxJ9BAHWnZjE5KsVbE-mN6jKrx8WnYrG