Our qualified team of NCC Certified - Electronic Fetal Monitoring study material to improve the quality and to match the changes in the syllabus and pattern shared by EFM. Our desktop NCC EFM Practice Exam software is designed for all those candidates who want to learn and practice in the actual NCC EFM exam environment.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Physiology | 11% | - Fetal cardiovascular physiology - Factors affecting fetal oxygenation - Uteroplacental function |
| Topic 2: Professional Issues | 5% | - Safety and quality improvement - Legal and ethical aspects - Documentation standards |
| Topic 3: Fetal Assessment and Methods | 9% | - Auxiliary assessment techniques - Correlation with clinical status - Indications for monitoring |
| Topic 4: Electronic Monitoring Equipment | 5% | - Proper application and use - Calibration and accuracy - Troubleshooting artifacts |
| Topic 5: Pattern Recognition and Intervention | 70% | - Interpretation per NICHD standards - Clinical decision-making and interventions - Tracing evaluation and management - Fetal heart rate patterns classification |
>> Reliable EFM Test Preparation <<
If you buy online classes, you will need to sit in front of your computer on time at the required time; if you participate in offline counseling, you may need to take an hour or two on the commute to class. But if you buy EFM exam material, things will become completely different. Certified - Electronic Fetal Monitoring study questions will provide you with very flexible learning time. Unlike other learning materials on the market, EFM exam guide has an APP version. You can download our app on your mobile phone. And then, you can learn anytime, anywhere. Whatever where you are, whatever what time it is, just an electronic device, you can practice. With Certified - Electronic Fetal Monitoring study questions, you no longer have to put down the important tasks at hand in order to get to class; with EFM Exam Guide, you don’t have to give up an appointment for study. Our study materials can help you to solve all the problems encountered in the learning process, so that you can easily pass the exam.
NEW QUESTION # 98
This tracing demonstrates: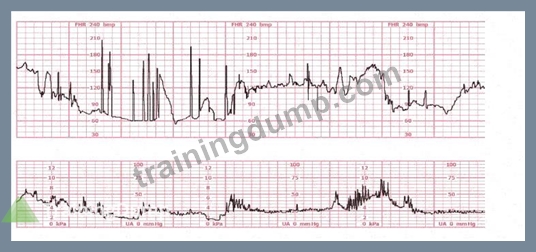
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
A prolonged deceleration is defined by NICHD and NCC as:
* A deceleration lasting #2 minutes but <10 minutes
* Decrease in FHR of #15 bpm
* Can occur with or without uterine contractions
This tracing shows:
* A deep drop in FHR down to ~60-70 bpm
* Duration lasting several minutes
* Recovery back to baseline
* Moderate variability present afterward
Because variability remains present and the tracing does not show:
* Absent variability
* Recurrent late decelerations
* Recurrent variable decelerations with absent variability
* Bradycardia for #10 minutes
...it does not meet criteria for Category III.
It is also not bradycardia, because bradycardia requires:
* Baseline <110 bpm for 10 minutes or longer
Therefore the correct interpretation is a prolonged deceleration.
References:NCC C-EFM Candidate Guide; NICHD FHR Definitions; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 99
Amnioinfusion can cause what changes in the fetal heart rate tracing?
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NCC defines amnioinfusion as indicated for:
* Recurrent variable decelerations caused by cord compression
* Oligohydramnios reducing buffer around the cord
Expected effect:
* Reduction or elimination of variable decelerations
Why the other answers are incorrect:
* A. Variability does not improve with amnioinfusion.
* B. Baseline FHR does not increase as a result of amnioinfusion.
Correct answer: C. Resolution of variable decelerations.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 100
A woman (G1, P0) at 41-weeks gestation presents to OB triage to rule out labor. Her cervical exam is 1 cm/50%/-2. Membranes are intact. She would like to go home if not in labor. Based on this tracing, which represents the last two hours, the best approach is: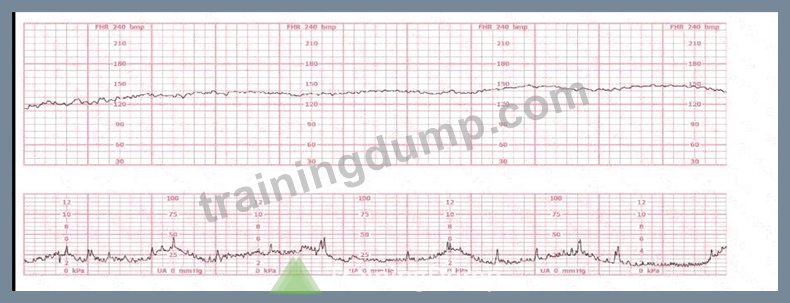
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The fetal heart rate tracing shows a normal baseline (120-150 bpm), moderate variability, and no decelerations, consistent with a Category I pattern. According to AWHONN's Fetal Heart Monitoring Principles & Practices and NCC Perinatal Safety recommendations, a Category I tracing reliably indicates normal fetal acid-base status at the time of assessment and is considered reassuring.
Simpson & Creehan emphasize that in triage, management decisions depend on cervical status, contraction pattern, membrane status, and fetal well-being. With a cervix at 1 cm/50%/-2, intact membranes, and no regular labor pattern, she is not in active or latent labor requiring admission, provided fetal status is reassuring.
Menihan states that a normal tracing lasting two hours with moderate variability supports safe discharge when maternal and fetal assessments are normal. Creasy & Resnik confirm that reassuring fetal testing plus absence of labor is appropriate for outpatient management.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 101
During the second stage of labor, a period of bradycardia develops. The fetal heart rate baseline variability is moderate. The most likely cause of this bradycardia is:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Second-stage bradycardia with moderate variability most commonly occurs from:
* Vagal stimulation caused by head compression, particularly during descent and pushing.
Moderate variability indicates:
* Neurologically intact fetus
* Sufficient oxygen reserve
* Temporary nature of bradycardia
This aligns with physiologic vagal slowing rather than hypoxic mechanisms.
Why the incorrect answers are wrong:
* A. Cord compression # typically produces variable decelerations, not sustained bradycardia with preserved variability.
* C. Vasospasm # associated with late decelerations and decreased variability (uteroplacental insufficiency).
Correct answer: B. Vagal stimulation
References:NCC Physiology Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 102
A nonstress test is nonreactive in a 36-week gestational age fetus. Vibroacoustic stimulation (VAS) is applied with no fetal response. The next step is to proceed to:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
A nonreactive NST with no response to vibroacoustic stimulation indicates:
* Possible fetal sleep cycle
* Possible CNS depression
* Possible hypoxemia
NCC, AWHONN, and MFM guidelines state the next step is a biophysical profile because:
* It evaluates fetal tone, movement, breathing, amniotic fluid, and NST
* Provides a complete assessment of fetal well-being
* Is less invasive and more informative than immediate delivery decisions Why the wrong answers are incorrect:
* B. Cesarean birth - not indicated without confirming fetal compromise.
* C. Induction of labor - not indicated until BPP clarifies fetal status.
Correct answer: A. Biophysical profile.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Creasy & Resnik; Simpson & Creehan.
NEW QUESTION # 103
......
Our company pays great attention to improve our EFM exam materials. Our aim is to develop all types study material about the official exam. Then you will relieve from heavy study load and pressure. Also, our researchers are researching new technology about the EFM Learning Materials. You will find that every detail of our EFM study braindumps is perfect and excellent not only on the content but also on the displays. And evey button on our website is easy, fast and convenient to use.
EFM Minimum Pass Score: https://www.trainingdump.com/NCC/EFM-practice-exam-dumps.html