P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by Real4Prep: https://drive.google.com/open?id=1bFruH9Dwl1eMyWyBy2IadZ_CZX6MTqgU
However, preparing for the EFM exam is not an easy job until they have real Certified - Electronic Fetal Monitoring (EFM) exam questions that are going to help them achieve this target. They have to find a trusted source such as Real4Prep to reach their goals. Get EFM Certified, and then apply for jobs or get high-paying job opportunities. If you think that EFM certification exam is easy to crack, you are mistaken.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Pattern Recognition and Intervention | 70% | - Tracing evaluation and management - Fetal heart rate patterns classification - Clinical decision-making and interventions - Interpretation per NICHD standards |
| Topic 2: Professional Issues | 5% | - Legal and ethical aspects - Documentation standards - Safety and quality improvement |
| Topic 3: Fetal Assessment and Methods | 9% | - Correlation with clinical status - Indications for monitoring - Auxiliary assessment techniques |
| Topic 4: Electronic Monitoring Equipment | 5% | - Proper application and use - Troubleshooting artifacts - Calibration and accuracy |
| Topic 5: Physiology | 11% | - Fetal cardiovascular physiology - Factors affecting fetal oxygenation - Uteroplacental function |
Dear every IT candidates, here, I will recommend Real4Prep EFM exam training material to all of you. If you use NCC EFM test bootcamp, you will not need to purchase anything else or attend other training. We promise that you can pass your EFM Certification at first attempt. The high pass rate has helped lots of IT candidates get their IT certification. In case of failure, we promise to give you full refund. No help, full refund!
NEW QUESTION # 98
(Full question statement)
The American College of Obstetricians and Gynecologists (ACOG) recommends continuous electronic fetal monitoring in pregnancies when there is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC relies heavily on ACOG Practice Bulletins for risk-based monitoring decisions. ACOG identifies maternal diabetes (pregestational or poorly controlled gestational diabetes) as a key high-risk obstetric condition warranting continuous electronic fetal monitoring due to risks such as fetal hypoxia, macrosomia, and metabolic complications.
In contrast, a history of preterm birth does not necessarily require continuous monitoring unless current pregnancy complications are present.
Macrosomia alone does not automatically justify continuous EFM unless accompanied by other risk factors.
Therefore, according to NCC-aligned ACOG clinical criteria, maternal diabetes is the correct indication.
NEW QUESTION # 99
A woman (G1P0) arrives in triage with a pain score of 4/10 at 39-weeks gestation. The fetal heart rate tracing shown is obtained. The best intervention is to: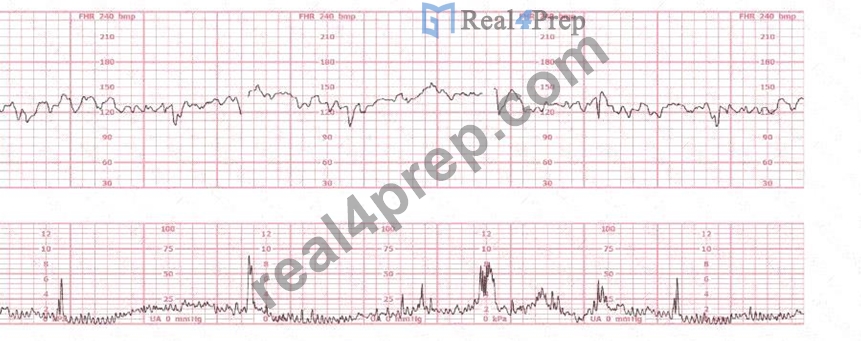
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing demonstrates a normal, reassuring fetal heart pattern that is technically categorized as Category I, indicating normal fetal acid-base status. Before any decision regarding discharge or induction, NCC emphasizes correct assessment of the tracing quality, fetal status, and uterine activity.
Key Tracing Characteristics
* Baseline:Approximately 135-145 bpm, well within the normal range of 110-160 bpm.
* Variability:The strip shows moderate variability (6-25 bpm), the strongest indicator of adequate fetal oxygenation per NCC, AWHONN, and NICHD.
* Accelerations:Several accelerations are present-another reassuring feature of normal fetal well-being.
* Decelerations:No variable, late, or prolonged decelerations are present.
* Uterine Activity:The lower channel shows poor recording quality and inconsistent signal- suggesting the toco is not capturing contractions well, not that the patient is contracting excessively or not at all.
Correct interpretation per NCC:
NCC emphasizes distinguishing between physiologic assessment and technical artifact.
The fetal tracing is completely reassuring.
The only abnormality is the poor uterine activity signal, a common triage occurrence due to:
* Toco placement
* Maternal body habitus
* Positioning
* Low contraction intensity in early labor
Thus, the correct next step is to optimize equipment (reposition the toco, adjust belt, palpate contractions) and continue to monitor.
Why the other options are incorrect:
B). Admit for induction - NOT indicated
* There is no evidence of fetal compromise.
* No indication for induction is present (pain score 4/10, reassuring FHR, term pregnancy).
* NCC emphasizes avoiding unnecessary interventions.
C). Discharge to home - NOT yet appropriate
* You cannot safely discharge a patient with a poorly monitored contraction pattern.
* Adequate assessment requires confirming uterine activity-after fixing the toco.
Therefore, the appropriate action is:
A). Adjust tocotransducer and continue to monitor.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; NICHD Definitions; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 100
Fetal heart rate variability results from normal variance in fetal:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Variability reflects the interplay of the autonomic nervous system-sympathetic and parasympathetic influences-on the fetal myocardium. NCC defines variability as variation in the R-R intervals on the fetal ECG.
Key points:
* Variability originates from beat-to-beat fluctuations in ventricular depolarization timing.
* These R-R interval changes result from baroreceptor and chemoreceptor responses, vagal modulation, and fetal behavioral states.
* Carbon dioxide levels affect chemoreceptors but do not directly define variability.
Thus, variability is best described as resulting from variance in R-R intervals.
References:NCC C-EFM Candidate Guide; NICHD Definitions; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring.
NEW QUESTION # 101
A woman at 36-weeks gestation comes in because of uterine contractions radiating to the back. She has no insurance. In accordance with the Emergency Medical Treatment and Active Labor Act (EMTALA), she is obligated to be:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC's Professional Issues domain includes EMTALA obligations for pregnant patients. EMTALA requires that ANY individual who presents to a hospital emergency department-regardless of insurance status- must receive:
* A Medical Screening Examination (MSE)
* Stabilization of any identified emergency medical condition (including labor)
* No transfer unless the patient requests it or the hospital cannot provide necessary stabilizing care This patient reports contractions at 36 weeks, which qualifies as a potential emergency medical condition until ruled out by the medical screening exam.
Correct obligations per EMTALA:
* She must NOT be transferred solely due to lack of insurance (option C).
* She does NOT need to be admitted unless labor is confirmed (option A).
* She must receive a medical screening examination and stabilization (option B).
Thus, the correct answer is B. Stabilized and receive a medical screening examination.
References:NCC C-EFM Candidate Guide (Professional Issues); EMTALA Statutory Requirements; AWHONN Fetal Heart Monitoring Principles & Practices.
NEW QUESTION # 102
The fetal heart rate tracing shown is consistent with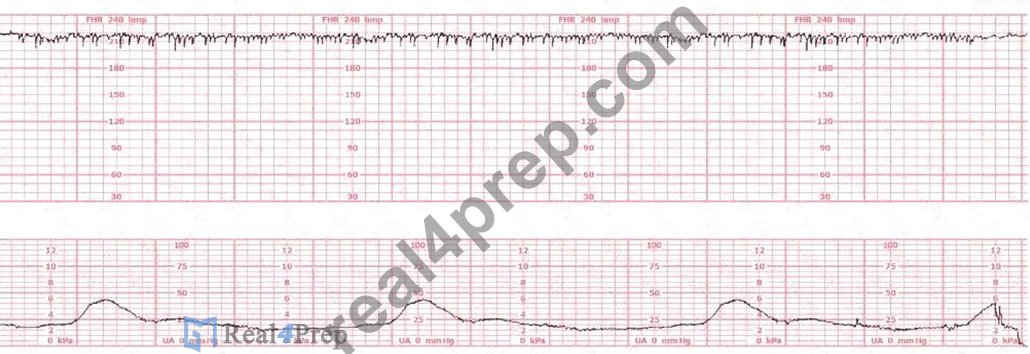
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The tracing demonstrates a very rapid, highly regular baseline fetal heart rate with minimal beat-to-beat variability-characteristic of fetal supraventricular tachycardia (SVT). NCC-recommended references, including AWHONN's Fetal Heart Monitoring Principles & Practices, Menihan's Electronic Fetal Monitoring: Concepts and Applications, Simpson & Creehan's Perinatal Nursing, and Creasy & Resnik's Maternal-Fetal Medicine all describe fetal SVT as a sustained tachyarrhythmia usually greater than 200 bpm
, narrow-complex, and extremely regular in appearance.
AWHONN teaches that SVT appears as a "tight, rapid, uniform baseline with minimal variability." Menihan states that "SVT may present on EFM as a nearly straight line due to the rapid, consistent rate with micro- oscillations." This differs significantly from artifact, which appears disorganized, erratic, and inconsistent in amplitude. Additionally, "half-counting" is a Doppler misinterpretation that records half of an extremely fast fetal rate, usually resulting in a falsely lower heart rate-not the very rapid tracing shown here.
Creasy & Resnik emphasize that SVT is the most common pathological fetal arrhythmia and can lead to fetal compromise if prolonged, making accurate recognition essential. Miller's Pocket Guide to Fetal Monitoring also identifies SVT as a pattern with a "smooth, fast rhythm lacking normal variability." All authoritative NCC-recommended references support that this EFM pattern is consistent with fetal SVT, not artifact or half-counting.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide to Fetal Monitoring
NEW QUESTION # 103
......
All formats of Real4Prep's products are immediately usable after purchase. We also offer up to 365 days of free updates so you can prepare as per the NCC EFM Latest Exam content. Real4Prep offers a free demo version of the NCC Certification Exams so that you can assess the validity of the product before purchasing it.
EFM Brain Dump Free: https://www.real4prep.com/EFM-exam.html
P.S. Free & New EFM dumps are available on Google Drive shared by Real4Prep: https://drive.google.com/open?id=1bFruH9Dwl1eMyWyBy2IadZ_CZX6MTqgU