BONUS!!! Download part of TestsDumps EFM dumps for free: https://drive.google.com/open?id=1wpBMClGQuUQqfHcDH4TJhdEz5uTLlYmK
TestsDumps actual EFM exam questions in PDF format are ideal for individuals who prefer to study on their tablets, laptops, and smartphones. Since these EFM exam questions can be studied from any place at any time, making this format a perfect alternative for candidates who are frequently on the move and want to prepare for the exam in a short time. Questions in the NCC EFM Pdf Format are printable, allowing you to prepare for the EFM test via hard copy. Our NCC EFM PDF version is regularly updated to improve the EFM exam questions based on the EFM real certification test’s content.
| Section | Objectives |
|---|---|
| Topic 1: Fetal Heart Rate Interpretation | - Accelerations and decelerations - Category I, II, and III tracing interpretation - Baseline rate and variability |
| Topic 2: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Topic 3: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Topic 4: Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Topic 5: Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Topic 6: Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
>> Reliable Exam EFM Pass4sure <<
Now you can think of obtaining any NCC certification to enhance your professional career. TestsDumps's EFM study guides are your best ally to get a definite success in EFM exam. The guides contain excellent information, exam-oriented questions and answers format on all topics of the certification syllabus. If you just make sure learning of the content in the guide, there is no reason of losing the EFM Exam.
NEW QUESTION # 76
A 30-year-old woman (G2P0) is experiencing preterm labor at 26-weeks gestation. She is receiving magnesium sulfate for neuroprotection. Her external fetal monitoring tracing over the past 30 minutes is shown. The next step would be to: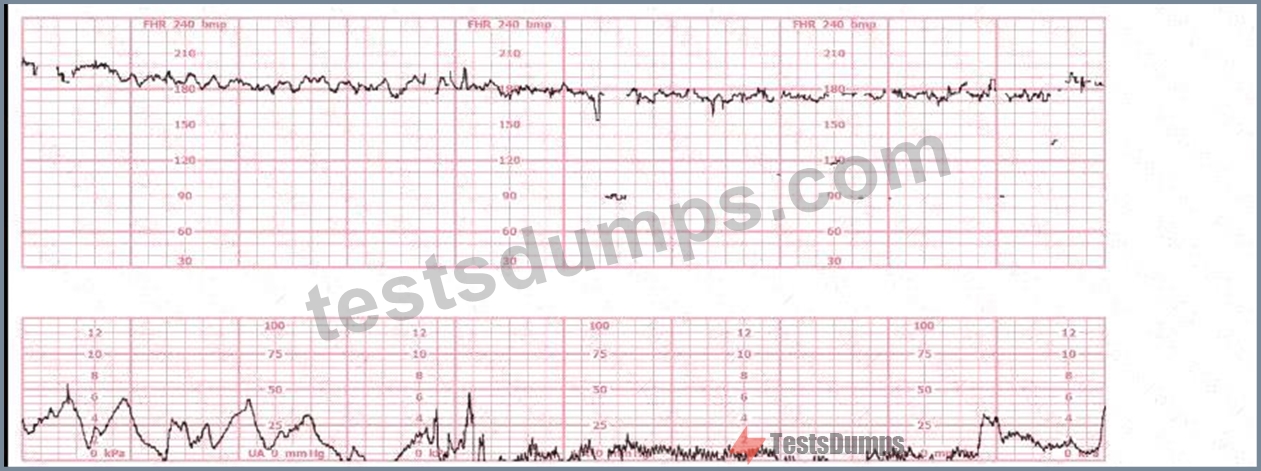
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline ~170-175 bpm # fetal tachycardia
* Minimal variability
* No contractions of significance
* Maternal treatment with magnesium sulfate, which typically decreases baseline and variability-not increase it NCC and AWHONN physiology guidelines emphasize that fetal tachycardia is most commonly associated with maternal infection, including chorioamnionitis, especially in preterm labor.
Magnesium sulfate does not cause tachycardia; it generally causes:
* # baseline
* # variability
Thus, fetal tachycardia + minimal variability in a preterm patient strongly suggests maternal infection, requiring evaluation for chorioamnionitis.
Why the wrong answers are incorrect:
* A. Acetaminophen # used after confirming fever, not before evaluating the cause.
* B. Discontinuing magnesium # magnesium sulfate does not cause tachycardia; discontinuing it removes fetal neuroprotection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Simpson & Creehan; Menihan EFM; Creasy & Resnik.
NEW QUESTION # 77
The ratio of oxyhemoglobin to the total amount of hemoglobin available is called oxygen
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Oxygen saturation refers to the percentage of hemoglobin binding sites occupied by oxygen. NCC physiology resources, including Simpson & Creehan and Creasy & Resnik, define oxygen saturation as the
"ratio of oxyhemoglobin to total hemoglobin"-the same definition used in fetal oxygenation discussions.
Oxygen affinity refers to hemoglobin's tendency to bind oxygen (related to the oxyhemoglobin dissociation curve).
Oxygen carrying capacity refers to the total amount of oxygen hemoglobin can transport, independent of current saturation.
AWHONN and Menihan emphasize that fetal oxygenation assessment is dependent on understanding oxygen saturation, not affinity or carrying capacity, when discussing fetal hypoxemia and gas exchange.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMenihan - EFM ConceptsMiller's Pocket Guide
NEW QUESTION # 78
(Full question statement)
A dysrhythmia is noted. The pregnancy and labor course has been normal with no complications. The next step in management is to
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC C-EFM sources: AWHONN, Miller's Pocket Guide, Menihan, Simpson, Creasy & Resnik, 2025 Candidate Guide) AWHONN and Menihan emphasize that most fetal dysrhythmias detected intrapartum are premature atrial contractions (PACs)-the most common benign rhythm variation. They typically appear as intermittent, irregular deflections on the fetal heart rate tracing without affecting variability or baseline.
Miller's Pocket Guide to Fetal Monitoring states that PACs are usually transient, self-limiting, and require only observation unless accompanied by tachyarrhythmia or hemodynamic compromise. When variability is preserved and no repetitive pattern or sustained tachycardia occurs, no intrauterine resuscitation measures are indicated.
Simpson and Creehan describe that oxygen administration and fluid boluses are not recommended for benign dysrhythmias, as they do not improve fetal conduction patterns and may contribute to unnecessary interventions.
The NCC 2025 Candidate Guide specifies that correct management requires distinguishing benign arrhythmias from pathologic tachyarrhythmias, which would require escalation. In the absence of fetal compromise or maternal pathology, the appropriate action is continued observation.
Therefore, the correct management is to continue to observe.
NEW QUESTION # 79
This fetal heart rate pattern is classified as Category III based on: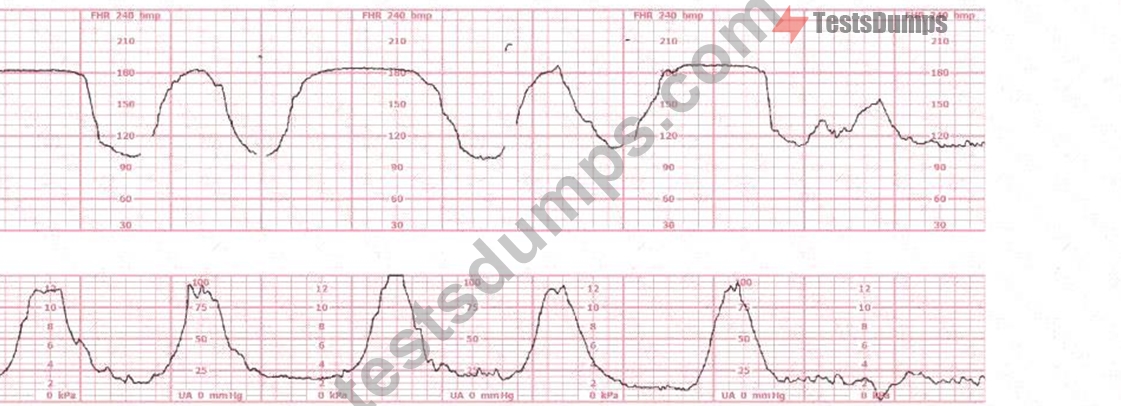
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing shows recurrent late decelerations accompanied by absent variability.
Per NICHD/NCC, a tracing is Category III if ANY of the following are present:
* Absent variability AND recurrent late decelerations
* Absent variability AND recurrent variable decelerations
* Absent variability AND bradycardia
* Sinusoidal pattern
In this strip:
* Variability is absent
* Decelerations are recurrent and late
The determining feature for the classification is absent variability, which indicates significant risk for fetal acidemia.
The contraction pattern (option B) does not determine category.
The deceleration type alone (option C) does not determine Category III without absent variability.
Thus, the classification is Category III because of absent variability.
References:NCC C-EFM Candidate Guide; NICHD Three-Tier System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring.
NEW QUESTION # 80
A fetal heart rate tracing is abnormal. A change in maternal position and oxygen administration do not correct the pattern. Following birth, a fetal cord blood sample is taken:
pH = 7.25
PaCO# = 46 mm Hg
PaO# = 20 mm Hg
HCO# = 22 mEq/L
Base deficit = -4 mEq/L
These results are best interpreted as:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Normal umbilical arterial values per NCC/AWHONN/Menihan:
* pH: 7.20-7.30
* PaCO#: 45-55 mmHg
* HCO#: 20-24 mEq/L
* Base deficit: 0 to -5 (normal to mild respiratory changes)
This sample shows:
* pH 7.25 # normal
* Base deficit -4 # no metabolic acidosis
* HCO# normal
* Slightly elevated PaCO#, consistent with mild respiratory influence but still normal
* PaO# 20 mmHg is normal for cord arterial blood
This profile is not acidotic (acidosis requires pH <7.10 and base deficit #12).
It also does not indicate hypoxia, which would present with metabolic acidosis.
Therefore: Normal.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 81
......
Everyone wants to stand out in such a competitive environment, but they don't know how to act. Maybe our EFM exam questions can help you. Having a certificate may be something you have always dreamed of, because it can prove that you have a certain capacity. Our EFM learning materials can provide you with meticulous help and help you get your certificate. Our EFM training prep is credible and their quality can stand the test. Therefore, our EFM practice materials can help you get a great financial return in the future and you will have a good quality of life.
Valid EFM Exam Prep: https://www.testsdumps.com/EFM_real-exam-dumps.html
P.S. Free & New EFM dumps are available on Google Drive shared by TestsDumps: https://drive.google.com/open?id=1wpBMClGQuUQqfHcDH4TJhdEz5uTLlYmK