BONUS!!! Download part of ValidExam EFM dumps for free: https://drive.google.com/open?id=1nfks5Ot6ML5FQen6NQ_CrhOJpJeMqlok
The ValidExam is committed to acing the Certified - Electronic Fetal Monitoring (EFM) exam questions preparation quickly, simply, and smartly. To achieve this objective ValidExam is offering valid, updated, and real Certified - Electronic Fetal Monitoring (EFM) exam dumps in three high-in-demand formats. These Certified - Electronic Fetal Monitoring (EFM) exam questions formats are PDF dumps files, desktop practice test software, and web-based practice test software.
| Section | Weight | Objectives |
|---|---|---|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
If you have been very panic sitting in the examination room, our EFM actual exam allows you to pass the exam more calmly and calmly. After you use our products, our study materials will provide you with a real test environment before the EFM exam. After the simulation, you will have a clearer understanding of the exam environment, examination process, and exam outline. Our EFM Study Materials will really be your friend and give you the help you need most. Our EFM exam materials understand you and hope to accompany you on an unforgettable journey.
NEW QUESTION # 77
A woman has been 5 cm dilated for the past 3 hours. The tracing shown has developed over the last 30 minutes. The best initial course of action is to: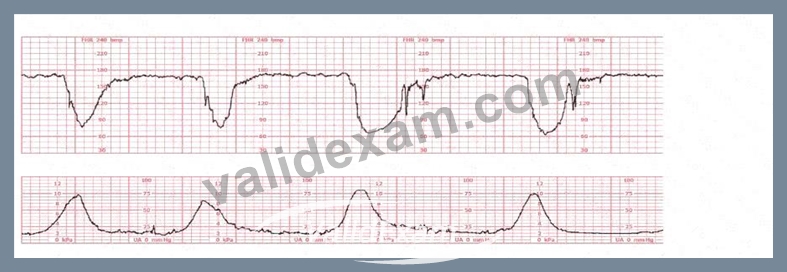
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The fetal heart rate tracing demonstrates recurrent deep variable decelerations with a rapid drop in FHR, a V-shaped pattern, and slow return to baseline. These are classic signs of cord compression. According to NCC, AWHONN, Miller, Menihan, and Simpson, recurrent variable decelerations require immediate intrauterine resuscitative interventions before any decision regarding operative birth.
NCC-aligned intervention steps include:
* Maternal repositioning (first-line for cord compression)
* Reducing or stopping oxytocin if infusing
* IV fluid bolus
* Amnioinfusion (if appropriate and recurrent deep variables persist)
* Oxygen only if other measures fail (per NCC/AWHONN updated guidance)
The cervix has remained unchanged at 5 cm for 3 hours (a prolonged latent or early active labor pattern), but the fetal tracing shows Category II-recurrent variable decelerations. Category II dictates corrective action, not immediate delivery unless it progresses to Category III.
Cesarean birth (option C) is reserved for:
* Persistent Category III
* Failure of intrauterine resuscitation
* Proven fetal intoleranceNone of these conditions have been met yet.
Thus, the correct initial management is B. Perform intrauterine resuscitative measures.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD FHR Definitions; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 78
Interventions undertaken to address fetal tachycardia are targeted at maximizing
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Fetal tachycardia is typically caused by maternal fever, dehydration, hypoxia, medications, infection, or fetal stress. AWHONN and Simpson & Creehan emphasize that management focuses on improving oxygen delivery across the placenta, which is governed by uteroplacental perfusion.
Menihan's EFM text states that "interventions for fetal tachycardia must address oxygen transfer by optimizing uteroplacental blood flow," including hydration, reducing uterine activity, maternal repositioning, and treating maternal fever.
Increasing maternal circulation alone is insufficient unless it improves placental blood flow. Enhancing fetal sympathetic tone is not a clinical goal and would worsen tachycardia.
Creasy & Resnik highlight that fetal heart rate abnormalities resolve when uteroplacental perfusion is restored, confirming this as the primary target of intervention.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 79
The fetal heart rate tracing shown demonstrates: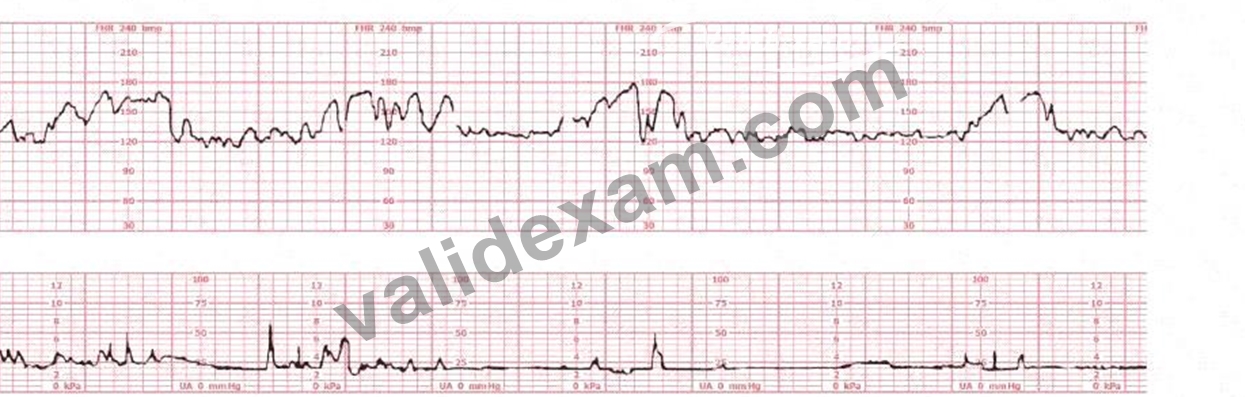
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC C-EFM uses NICHD terminology to describe key FHR characteristics: baseline, variability, accelerations, and decelerations. In this strip, the following findings are present:
* Baseline:The baseline appears approximately 135-145 bpm, which is within the normal 110-160 bpm range described in NCC and AWHONN materials.
* Variability:Beat-to-beat fluctuation is within 6-25 bpm, which meets the definition of moderate variability. NCC and NICHD define moderate variability as amplitude range of 6-25 bpm; this is associated with adequate fetal oxygenation and a normal fetal acid-base status.
* Accelerations:The tracing shows distinct increases in FHR above the baseline by at least 15 bpm lasting 15 seconds or more but less than 2 minutes. NCC and NICHD define an acceleration in a term fetus precisely as "a visually apparent abrupt increase in FHR, with peak #15 bpm above baseline, lasting #15 seconds and <2 minutes." The pattern shown fits this definition clearly.
* Category determination:A tracing with normal baseline, moderate variability, and accelerations without decelerations is classified as Category I, not Category II. Category II is reserved for tracings that are not clearly Category I or III, such as minimal or marked variability, recurrent variables, or prolonged decelerations.
* Marked variability consideration:Marked variability is defined as amplitude >25 bpm. While the tracing is somewhat jagged, the fluctuation does not sustain >25 bpm amplitude over a 10-minute segment and instead remains in the moderate range, so it does not meet criteria for marked variability.
Given these observations, the most accurate description of the tracing from the options provided is that it demonstrates accelerations.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 80
(Full question statement)
This tracing is consistent with: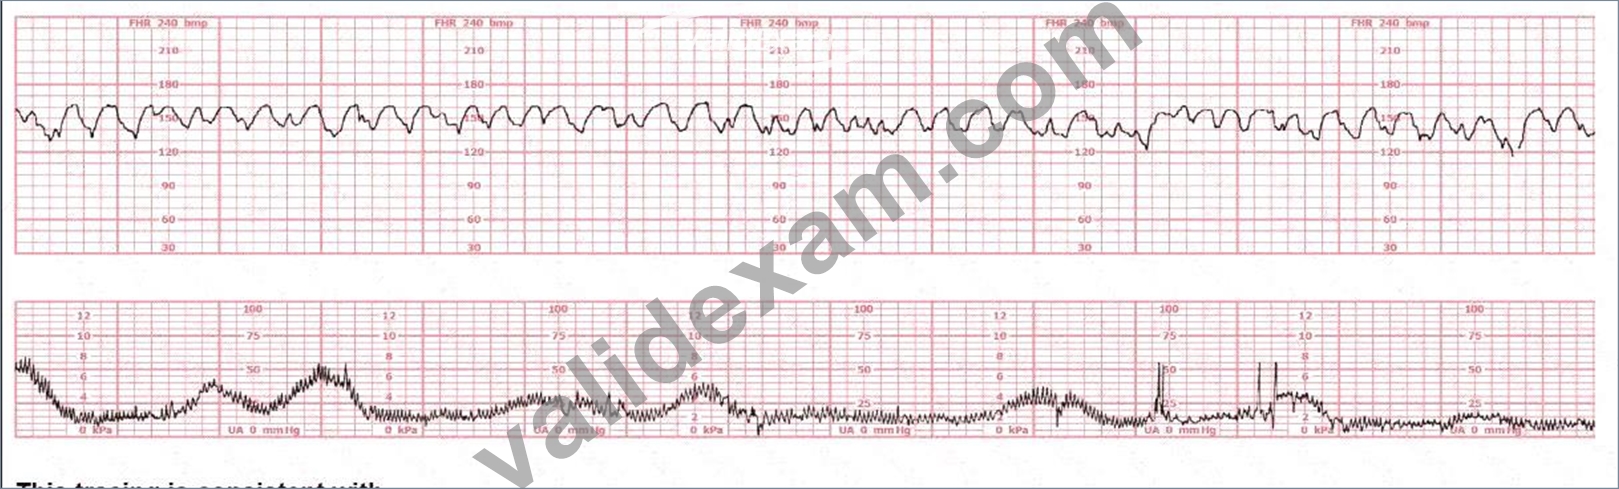
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC and AWHONN teaching materials describe that butorphanol, an opioid analgesic, characteristically produces a transient sinusoidal-like pattern or pseudo-sinusoidal pattern with moderate variability preserved.
This drug-related pattern has:
* smooth, regular oscillations
* maintained variability
* absence of true periodic decelerations
* resolution within 20-60 minutes
Simpson & Menihan describe butorphanol as producing a "saw-tooth, wavering pattern" often mistaken for dysrhythmia but actually benign.
True sinusoidal patterns (e.g., fetal-maternal hemorrhage) are fixed, smooth, non-variable patterns with absent variability, not matching the scenario.
Atrial flutter produces very rapid atrial contractions, which manifest as irregular baseline spikes-also not consistent.
Therefore, the described tracing aligns most closely with butorphanol effects.
NEW QUESTION # 81
An electronic fetal monitoring factor that best correlates with fetal well-being is:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The single best indicator of fetal oxygenation and neurologic integrity is:
* Moderate baseline variability
Variability reflects:
* Normal autonomic regulation
* Adequate fetal oxygenation
* Intact neurologic pathways
Absence of decelerations is helpful but not as predictive.
Baseline FHR (e.g., 140-150) is normal, but baseline alone does not confirm well-being.
Correct answer: C. Presence of variability
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; NICHD Definitions; Simpson & Creehan.
NEW QUESTION # 82
......
Desktop and web-based EFM practice exams are available at ValidExam for thorough preparation. Going through these NCC EFM mock exams boosts your learning and reduces mistakes in the NCC EFM Test Preparation. Customization features of NCC EFM practice tests allow you to change the settings of the EFM test sessions.
EFM Test Quiz: https://www.validexam.com/EFM-latest-dumps.html
DOWNLOAD the newest ValidExam EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1nfks5Ot6ML5FQen6NQ_CrhOJpJeMqlok