BTW, DOWNLOAD part of Free4Torrent MCCQE dumps from Cloud Storage: https://drive.google.com/open?id=15VxywflcAWAAUf05BHMstK4HTEWUgxP1
Free4Torrent offers MCCQE Part 1 Exam (MCCQE) practice exams (desktop & web-based) which are customizable. It means candidates can set time and Medical Council of Canada MCCQE questions of the MCCQE practice exam according to their learning needs. The Real MCCQE Exam environment of practice test help test takers to get awareness about the test pressure so that they become capable to counter this pressure during the final exam.
| Section | Objectives |
|---|---|
| Topic 1: Dimensions of Care | - Chronic Care
|
| Topic 2: Physician Activities | - Communication
|
There are many benefits that make Exams. Medical Council of Canada is the best platform for study material. There is customer support available to solve any issues you may face. You can try a free demo version of the Medical Council of Canada MCCQE exam preparation material. In case of unsatisfactory results, we offer a full refund guarantee (terms and conditions apply). We also offer up to 12 months of free Valid MCCQE Exam Questions updates. Buy our product today and get these benefits.
NEW QUESTION # 353
A 14-month-old boy is brought to see you for a well-baby check-up and is noted to have onlyone testis.
Ultrasound confirms an undescended testis. Which one of the following is the best next step?
Answer: C
Explanation:
Orchiopexy is the treatment of choice for cryptorchidism and should be performed between 6-18 months of age. Early surgery improves fertility outcomes and reduces malignancy risk.
Toronto Notes 2023 - Pediatrics, Urology:
"Undescended testes should be referred for orchiopexy ideally before 18 months of age. Observation beyond
6 months is not recommended."
MCCQE1 Objectives - Pediatrics > Genitourinary Disorders:
"Candidates must recognize and refer for cryptorchidism early to optimize testicular function and reduce cancer risk." Hormonal therapies (C, D) are not recommended due to limited efficacy. Observation (A) is too late beyond
NEW QUESTION # 354
An 80-year-old woman presents to the Emergency Department with dizziness. She has a medical history of coronary artery disease. On examination, she is alert and oriented. Her vital signs are as follows:
Her electrocardiogram is shown in the image.
Which one of the following is the most likely diagnosis?
Blood pressure
80/60 mm Hg
Heart rate
40/min
Respiratory rate
12/min
Her electrocardiogram is shown in the attached image. Which one of the following is the most likely diagnosis?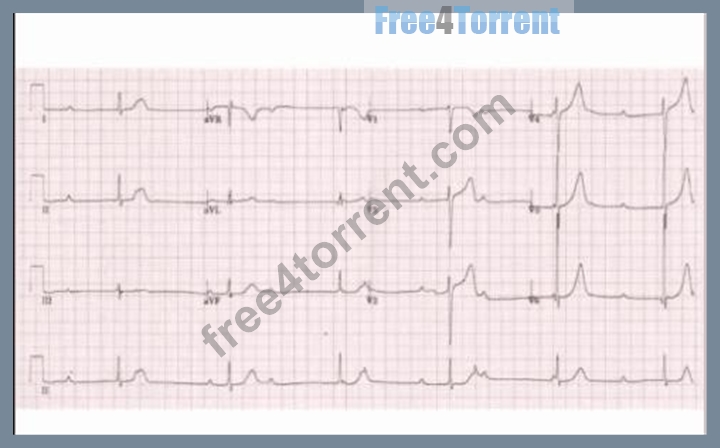
Answer: E
Explanation:
Comprehensive and Detailed Explanation:
The ECG reveals:
Regular P waves that are not consistently followed by QRS complexes
A dissociation between the atrial (P wave) and ventricular (QRS complex) activity A slow ventricular rate (~40 bpm) independent of atrial rate These findings are characteristic of a third-degree (complete) atrioventricular (AV) block, where there is no conduction of atrial impulses to the ventricles. The atria and ventricles beat independently, and the ventricular rate is maintained by an escape rhythm, often junctional or ventricular in origin.
This correlates with the patient's symptoms (dizziness, hypotension) and bradycardia, suggesting inadequate cardiac output due to AV dissociation.
Toronto Notes 2023 - Cardiology:
"Third-degree AV block shows complete AV dissociation with independent atrial and ventricular activity. It typically presents with bradycardia and hypotension. Urgent pacing may be required." MCCQE1 Objectives (Cardiology > 34-2: Bradyarrhythmias and Conduction Disorders):
"Candidates must identify complete heart block and recognize its clinical urgency." Ruling out other options:
A). Sinus bradycardia would show regular P waves with 1:1 P-QRS conduction.
B). First-degree AV block has prolonged PR intervals ( > 200 ms) but all P waves are conducted.
D). Junctional escape rhythm may present with bradycardia, but P waves would be absent, inverted, or occur after QRS complexes.
E). Mobitz type I (Wenckebach) has progressively lengthening PR intervals before a dropped QRS.
NEW QUESTION # 355
A 67-year-old farmer presents with a 6-month history of progressive weakness in both arms. He now has difficulty in climbing but says he can still drive his tractor. Examination shows slight but definite atrophy of muscles of pectoral girdle, especially over his scapula. Fasciculations are visible. There is hyperreflexia of most tendon reflexes of arms and legs, left ankle clonus and left Babinski reflex. Which one of the following is the most likely diagnosis?
Answer: B
Explanation:
This presentation is most consistent with amyotrophic lateral sclerosis (ALS), characterized by progressive degeneration of both upper motor neurons (UMN) and lower motor neurons (LMN). The patient has LMN signs in the upper limbs-muscle atrophy of the shoulder girdle and visible fasciculations-alongside UMN signs-hyperreflexia, ankle clonus, and a Babinski reflex. The combination of UMN and LMN findings in multiple body regions with a gradual, progressive course over months strongly supports ALS. Multiple sclerosis typically produces disseminated neurologic deficits separated in time and space and does not usually cause prominent fasciculations or progressive LMN wasting. Cerebellar degeneration causes ataxia, dysmetria, and gait instability rather than mixed UMN/LMN signs. A pontine astrocytoma would more often cause cranial nerve deficits and brainstem signs and is less likely to present as a diffuse, progressive mixed motor neuron syndrome in an older adult. Parkinson disease causes bradykinesia, rigidity, and resting tremor, not Babinski or fasciculations. MCCQE objectives emphasize recognizing mixed UMN/LMN patterns and identifying ALS as a key progressive motor neuron disorder.
NEW QUESTION # 356
An 80-year-old woman presents to the Emergency Department with dizziness. She has a medical history of coronary artery disease. On examination, she is alert and oriented. Her vital signs are as follows:
Her electrocardiogram is shown in the image.
Which one of the following is the most likely diagnosis?
Blood pressure
80/60 mm Hg
Heart rate
40/min
Respiratory rate
12/min
Her electrocardiogram is shown in the attached image. Which one of the following is the most likely diagnosis?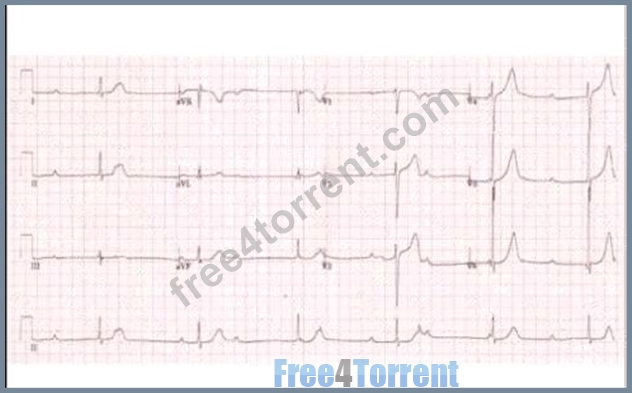
Answer: E
Explanation:
Comprehensive and Detailed Explanation:
The ECG reveals:
* Regular P waves that are not consistently followed by QRS complexes
* A dissociation between the atrial (P wave) and ventricular (QRS complex) activity
* A slow ventricular rate (~40 bpm) independent of atrial rate
These findings are characteristic of a third-degree (complete) atrioventricular (AV) block, where there is no conduction of atrial impulses to the ventricles. The atria and ventricles beatindependently, and the ventricular rate is maintained by an escape rhythm, often junctional or ventricular in origin.
This correlates with the patient's symptoms (dizziness, hypotension) and bradycardia, suggesting inadequate cardiac output due to AV dissociation.
Toronto Notes 2023 - Cardiology:
"Third-degree AV block shows complete AV dissociation with independent atrial and ventricular activity. It typically presents with bradycardia and hypotension. Urgent pacing may be required." MCCQE1 Objectives (Cardiology > 34-2: Bradyarrhythmias and Conduction Disorders):
"Candidates must identify complete heart block and recognize its clinical urgency." Ruling out other options:
* A. Sinus bradycardia would show regular P waves with 1:1 P-QRS conduction.
* B. First-degree AV block has prolonged PR intervals (>200 ms) but all P waves are conducted.
* D. Junctional escape rhythm may present with bradycardia, but P waves would be absent, inverted, or occur after QRS complexes.
* E. Mobitz type I (Wenckebach) has progressively lengthening PR intervals before a dropped QRS.
NEW QUESTION # 357
A 22-year-old woman is brought to the Emergency Department by her boyfriend, who says that she is experiencing a fentanyl overdose. She is unresponsive and cyanotic. She regains consciousness after naloxone is injected intravenously and demonstrates no further respiratory depression during 8 hours of observation.
She states that she is 22 weeks' pregnant and wants to stop using opioids. Which one of the following is the best next step?
Answer: B
Explanation:
For pregnant patients with opioid use disorder, opioid agonist therapy with methadone or buprenorphine is the standard of care. Detoxification is not recommended in pregnancy due to increased risk of fetal distress, preterm labor, and relapse. Methadone reduces illicit opioid use and stabilizes both mother and fetus.
Toronto Notes 2023 - Addiction Medicine / Obstetrics:
"Methadone maintenance therapy is the treatment of choice for pregnant patients with opioid use disorder.
Detoxification is not advised during pregnancy due to relapse risk and potential harm to the fetus." MCCQE1 Objectives (Obstetrics > 80-3: Substance Use in Pregnancy):
"Candidates must manage opioid use disorder in pregnancy with evidence-based therapies, including referral for methadone or buprenorphine." Counselling alone (D) is insufficient as first-line therapy. Home detox (C) is unsafe. Inpatient detox (A) is not recommended in pregnancy.
NEW QUESTION # 358
......
Our company is responsible for our MCCQE Part 1 Exam exam cram. Every product we have sold to customer will enjoy considerate after-sales service. If you have problems about our MCCQE test guide such as installation, operation and so on, we will quickly reply to you after our online workers have received your emails. We are not afraid of troubles. We warmly welcome to your questions and suggestions. Now that you have spent money on our MCCQE Exam Questions, we have the obligation to ensure your comfortable learning. We do not have hot lines. So you are advised to send your emails to our email address. In case you send it to others’ email inbox, please check the address carefully before. The after-sales service of our MCCQE exam questions can stand the test of practice. Once you trust our products, you also can enjoy such good service.
Latest MCCQE Exam Vce: https://www.free4torrent.com/MCCQE-braindumps-torrent.html
P.S. Free & New MCCQE dumps are available on Google Drive shared by Free4Torrent: https://drive.google.com/open?id=15VxywflcAWAAUf05BHMstK4HTEWUgxP1