The experts in our company have been focusing on the CCDS examination for a long time and they never overlook any new knowledge. The content of our CCDS study materials has always been kept up to date. We will inform you by E-mail when we have a new version. With our great efforts, our CCDSpractice dumps have been narrowed down and targeted to the CCDS examination. We can ensure you a pass rate as high as 99%!
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Quality, Risk Adjustment & Health Initiatives | 15% | - Quality reporting, public reporting, and compliance programs - Severity of Illness (SOI) / Risk of Mortality (ROM) - Risk adjustment models and documentation impact |
| Topic 2: Clinical Knowledge & Disease Processes Application | 20% | - Disease processes across body systems applied to chart review - Clinical indicators, lab results, medications, diagnostic findings - Medical terminology, anatomy, physiology, pathophysiology |
| Topic 3: Clinical Documentation Review & Query Practices | 20% | - Documentation gap identification and resolution - Concurrent and retrospective chart review methodologies - Query development, communication, and ethical standards |
| Topic 4: Coding Guidelines & Official Reporting Standards | 15% | - AHIMA/ACDIS Guidelines for Compliant Query Practice - ICD-10-CM/PCS Official Guidelines for Coding and Reporting - Coding integrity and compliant documentation practices |
| Topic 5: Healthcare Regulations, Reimbursement & Documentation Requirements – IPPS | 15% | - Documentation responsibilities of medical and clinical staff - Inpatient Prospective Payment System (IPPS) fundamentals - Medicare Severity Diagnostic Related Groups (MS-DRGs) |
| Topic 6: CDI Program Management & Professional Practice | 15% | - Program metrics, benchmarks, and performance measurement - Ethics, HIPAA, and professional conduct - Provider education and training strategies |
We have authoritative production team made up by thousands of experts helping you get hang of our Certified Clinical Documentation Specialist study question and enjoy the high quality study experience. We will update the content of CCDS test guide from time to time according to recent changes of examination outline and current policies, so that every examiner can be well-focused and complete the exam focus in the shortest time. We will provide high quality assurance of CCDS Exam Questions for our customers with dedication to ensure that we can develop a friendly and sustainable relationship.
NEW QUESTION # 34
The table below shows physician performance: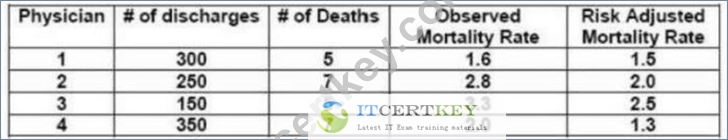
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
Answer: B
Explanation:
Physician 4 has the most favorable risk-adjusted mortality rate, at 1.3, compared with Physician 1 at 1.5, Physician 2 at 2.0, and Physician 3 at 2.5. Although Physician 1 has fewer observed deaths and an observed mortality rate of 1.6%, public outcome comparisons commonly incorporate risk adjustment rather than relying solely on raw mortality. Risk adjustment attempts to account for differences in patient complexity, comorbid disease burden, demographic factors, and other characteristics that influence expected outcomes.
This is directly relevant to CDI because incomplete documentation of clinically significant comorbidities can understate patient severity and therefore adversely affect the expected mortality component of risk-adjusted performance calculations. Conversely, accurate documentation allows coded data to represent the actual severity and risk of the population being treated. Healthgrades specifically states that its mortality methodology adjusts for patient risk factors to permit more meaningful comparisons of clinical outcomes.
The CCDS content outline specifically requires knowledge of mortality indices, severity of illness/risk of mortality, physician performance, and the effect of documentation on publicly reported data.
CCDS Reference Topics: Impact of reportable diagnoses on quality of care; Healthcare facility CDI program analysis; mortality index and risk adjustment.
=========
NEW QUESTION # 35
A physician documents obesity. A registered dietitian records a BMI of 38.4 kg/m². Which statement is MOST accurate?
Answer: A
NEW QUESTION # 36
A CDI team identifies that orthopedic surgeons frequently document "postoperative anemia" without specifying whether blood loss is acute, expected, chronic, or clinically insignificant. What is the BEST educational strategy?
Answer: B
Explanation:
The strongest educational approach is targeted specialty-specific education using the surgeons' own documentation trends and realistic clinical examples. This addresses the recurring documentation problem while remaining clinically relevant to the audience.
Orthopedic surgeons do not need to become coding specialists. Education should instead explain which clinical distinctions matter-for example, whether anemia represents expected postoperative change, acute blood loss anemia, chronic anemia, or another diagnosis-and why accurate terminology improves the medical record.
Providing a long code list is unlikely to improve physician documentation behavior. Instructing surgeons to document acute blood loss anemia whenever hemoglobin decreases would be clinically inappropriate and could produce unsupported diagnoses. A postoperative hemoglobin decline may reflect hemodilution, expected surgical blood loss, chronic anemia, or other factors.
Stopping queries would leave meaningful ambiguities unresolved.
ACDIS/AHIMA query guidance emphasizes documentation accuracy and provider independence rather than reimbursement-focused diagnosis selection.
Successful physician education should be concise, clinically oriented, supported by service-line data, and reinforced when subsequent query trends demonstrate persistent problems.
CCDS Reference Topics: Physician education; communication; postoperative anemia; query trends; provider engagement.
=========
NEW QUESTION # 37
A registered dietitian documents severe malnutrition based on substantial weight loss, severe muscle depletion, and prolonged inadequate energy intake. The attending physician documents only "poor oral intake." What is the BEST action for the CDI specialist?
Answer: D
Explanation:
The appropriate action is to query the provider regarding the patient's nutritional diagnosis. The dietitian's assessment supplies important clinical evidence, but the associated diagnosis of malnutrition generally must be documented by an appropriate provider before the diagnosis code is assigned.
The FY 2026 ICD-10-CM Official Guidelines permit selected elements to come from non-provider clinicians-such as BMI, pressure-ulcer stage, coma scale, NIH Stroke Scale, certain social determinants, and other specifically identified exceptions. Malnutrition diagnosis itself is not simply assigned solely from a dietitian's diagnostic statement under this general rule.
Ignoring the dietitian's findings would also be inappropriate. CDI review should integrate multidisciplinary documentation because such documentation can reveal valid clarification opportunities. Severe weight loss, reduced intake, and documented muscle depletion provide a clinical basis for a neutral query.
The query should not state that severe malnutrition "must" be documented because it is an MCC. Instead, it should present the relevant nutrition findings and allow the provider to determine the diagnosis, including severe malnutrition, another level of malnutrition, another cause, or inability to determine.
CCDS Reference Topics: Malnutrition; multidisciplinary documentation; provider diagnosis requirements; clinical indicators.
=========
NEW QUESTION # 38
A physician responds to a clinically supported CDI query by stating that the proposed diagnosis does not apply and documents a different diagnosis supported by the patient's condition. What is the BEST action by the CDI specialist?
Answer: D
Explanation:
The CDI specialist should respect the provider's independent clinical judgment, provided the response clearly addresses the query and the resulting documentation is clinically coherent.
A query is a request for clarification-not a mechanism for compelling the provider to select CDI's preferred diagnosis. Physician disagreement is therefore not inherently a failed query. The provider may appropriately document another condition, rule out a suspected condition, or explain why the indicators have another clinical interpretation.
Repeatedly querying until a desired diagnosis appears creates serious compliance risk and can undermine the integrity of the documentation process. Escalation may be appropriate in defined circumstances-for example, unresolved contradictions, unanswered high-priority queries, or persistent clinical-validation issues-but should follow organizational policy and should not occur merely because CDI dislikes the provider's answer.
The 2026 ACDIS/AHIMA guidance is the current foundational query-practice standard and emphasizes compliant clarification across healthcare settings.
Effective CDI communication requires clinical knowledge, professional dialogue, and recognition that final diagnostic determinations belong to the responsible provider.
CCDS Reference Topics: Physician communication; query responses; provider independence; escalation; professional conduct.
=========
NEW QUESTION # 39
......
If you do not get a reply from our service, you can contact customer service again. The staff of CCDS study guide is professionally trained. They can solve any problems you encounter on the CCDS exam questions. Of course, their service attitude is definitely worthy of your praise. I believe that you are willing to chat with a friendly person. All of CCDS Learning Materials do this to allow you to solve problems in a pleasant atmosphere while enhancing your interest in learning.
Brain Dump CCDS Free: https://www.itcertkey.com/CCDS_braindumps.html