BONUS!!! Download part of ActualTorrent CIC dumps for free: https://drive.google.com/open?id=1nhHoHtpgTlJKxGIEAumvvw0xRez4J37E
After you purchase our CIC study materials, we will provide one-year free update for you. Within one year, we will send the latest version to your mailbox with no charge if we have a new version of CIC learning materials. We will also provide some discount for your updating after a year if you are satisfied with our CIC Exam Questions. And if you find that your version of the CIC practice guide is over one year, you can enjoy 50% discount if you buy it again.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Preventing/Controlling the Transmission of Infectious Agents | 17-19% | |
| Topic 2: Employee/Occupational Health | 10-13% | |
| Topic 3: Environment of Care | 10-13% | |
| Topic 4: Identification of Infectious Disease Processes | 17-19% | |
| Topic 5: Surveillance and Epidemiologic Investigation | 22-26% | |
| Topic 6: Cleaning, Sterilization, Disinfection, Asepsis | 10-13% | |
| Topic 7: Management and Communication | 10-13% | |
| Topic 8: Education and Research | 6-9% |
>> CIC Certification Test Answers <<
The ActualTorrent is one of the top-rated and renowned platforms that has been offering real and valid CBIC Certified Infection Control Exam (CIC) exam practice test questions for many years. During this long time period countless CBIC Certified Infection Control Exam (CIC) exam candidates have passed their dream CIC certification and they are now certified CBIC professionals and pursuing a rewarding career in the market.
NEW QUESTION # 90
A city has a population of 150.000. Thirty new cases of tuberculosis (TB) were diagnosed in the city last year.
These now cases brought the total number of active TB cases in the city last year to 115. Which of the following equations represents the incidence rate tor TB per 100.000 in that year?
Answer: D
Explanation:
The incidence rate is calculated using the formula:
A white paper with black text AI-generated content may be incorrect.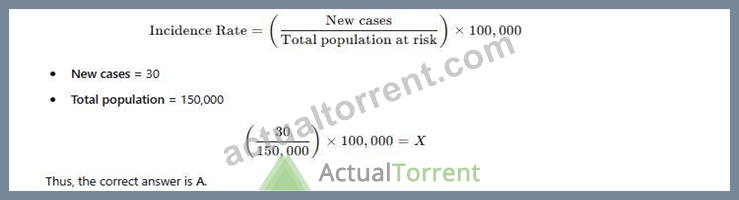
Why the Other Options Are Incorrect?
* B. (30 ÷ 150,000) × 100 = X - Incorrect multiplier (should be 100,000 for standard incidence rate).
* C. (115 ÷ 150,000) × 100,000 = X - 115 represents total cases (prevalence), not incidence.
* D. (115 ÷ 100,000) × 100 = X - Uses the wrong denominator and multiplier.
CBIC Infection Control Reference
APIC defines the incidence rate as the number of new cases per population unit, typically per 100,000 people.
NEW QUESTION # 91
The infection preventionist (IP) is working with Environmental Services to evaluate a new disinfectant for purchase by the facility. With which of the following should the IP be MOST concerned?
Answer: B
Explanation:
When evaluating a new disinfectant, theinfection preventionist's primary concern must be the safety and effectiveness of the product. This includes ensuring the product is EPA-registered, effective against targeted pathogens, safe for both the environment and users, and compliant with regulatory guidelines.
* From theAPIC/JCR Workbook, key considerations include:
"Organizations should evaluate each product to ensure that it can be used safely and include a review of dilutions, storage, shelf life, PPE needed, and disposal and ventilation requirements to ensure that OSHA, EPA, or local requirements are met".
* TheCBIC Study Guidereinforces that:
"Safety and efficacy are critical factors in evaluating new products, with particular emphasis on infection prevention and user safety".
* The other options, while relevant, are not the most critical factors in determining product adoption from an infection control standpoint.
References:
APIC/JCR Workbook, 4th Edition, Chapter 8 - Disinfection and Sterilization CBIC Study Guide, 6th Edition, Product Evaluation Section
NEW QUESTION # 92
Which of the following findings indicates that a sputum sample has been properly collected from a patient with possible bacterial pneumonia?
Answer: D
Explanation:
The CBIC Certified Infection Control Exam Study Guide (6th edition) explains that the quality of a sputum specimen is critical for accurate diagnosis of bacterial pneumonia. A properly collected sputum sample should originate from the lower respiratory tract, not from saliva or the oropharynx. Microscopic examination of the specimen-typically using a Gram stain-is used to assess specimen adequacy before culture results are interpreted.
A high-quality sputum specimen is characterized by numerous neutrophils and few or no squamous epithelial cells. Neutrophils indicate an inflammatory response in the lower airways, consistent with bacterial infection.
In contrast, epithelial cells originate from the mouth and upper respiratory tract; a large number of epithelial cells suggests contamination with saliva and an improperly collected specimen.
Option A correctly describes these criteria and therefore indicates proper specimen collection. Option C reflects poor-quality sputum contaminated with oral secretions and should be rejected or recollected. Option B (presence of blood) may occur in pneumonia but does not indicate specimen quality. Option D is nonspecific and may represent contamination or colonizing flora rather than true infection.
For the CIC exam, it is important to recognize that specimen validity precedes interpretation of microbiologic results. The presence of abundant neutrophils with minimal epithelial cells confirms that the sputum sample is appropriate for diagnosing bacterial pneumonia and supports accurate clinical and epidemiologic decision-making.
NEW QUESTION # 93
A 36-year-old female presents to the Emergency Department with a petechial rash, meningitis, and cardiac arrest. During the resuscitation, a phlebotomist sustained a needlestick injury. The next day, blood cultures reveal Neisseria meningitidis. The exposure management for the phlebotomist is:
Answer: C
Explanation:
The scenario involves a needlestick injury sustained by a phlebotomist during the resuscitation of a patient diagnosed with Neisseria meningitidis infection, characterized by a petechial rash, meningitis, and cardiac arrest. Neisseria meningitidis is a gram-negative diplococcus that can cause meningococcal disease, including meningitis and septicemia, and is transmitted through direct contact with respiratory secretions or, in rare cases, blood exposure. The exposure management for the phlebotomist must align with infection control guidelines, such as those from the Certification Board of Infection Control and Epidemiology (CBIC) and the CDC, to prevent potential infection. Let's evaluate each option:
* A. Prophylactic rifampin plus isoniazid: Prophylactic antibiotics are recommended for close contacts of individuals with meningococcal disease to prevent secondary cases. Rifampin is a standard prophylactic agent for Neisseria meningitidis exposure, typically administered as a 2-day course (e.g., 600 mg every
12 hours for adults). Isoniazid, however, is used for tuberculosis (TB) prophylaxis and is not indicated for meningococcal disease. Combining rifampin with isoniazid is incorrect, as it reflects a confusion with TB management rather than meningococcal exposure. This option is not appropriate.
* B. A tuberculin skin test now and in ten weeks: A tuberculin skin test (TST) or interferon-gamma release assay (IGRA) is used to screen for latent tuberculosis infection, with a follow-up test at 8-10 weeks to detect conversion after potential TB exposure. Neisseria meningitidis is not related to TB, and a needlestick injury from a meningococcal patient does not warrant TB testing. This option is irrelevant to the scenario and not the correct exposure management.
* C. Work furlough from day ten to day 21 after exposure: Neisseria meningitidis has an incubation period of 2-10 days, with a maximum of about 14 days in rare cases. The CDC and WHO recommend that healthcare workers exposed to meningococcal disease via needlestick or mucosal exposure be monitored for signs of infection (e.g., fever, rash) and, if symptomatic, isolated and treated.
Additionally, a work restriction or furlough from day 10 to day 21 after exposure is advised to cover the potential incubation period, especially if prophylaxis is declined or contraindicated. This allows time to observe for symptoms and prevents transmission to vulnerable patients. This is a standard infection control measure and the most appropriate initial management step pending prophylaxis decision.
* D. A review of the phlebotomist's hepatitis B vaccine status: Reviewing hepatitis B vaccine status is a critical step following a needlestick injury, as hepatitis B can be transmitted through blood exposure.
However, this applies to bloodborne pathogens (e.g., HBV, HCV, HIV) and is not specific to Neisseria meningitidis, which is primarily a respiratory or mucosal pathogen. While hepatitis B management (e.
g., post-exposure prophylaxis with hepatitis B immunoglobulin or vaccine booster) should be addressed as part of a comprehensive needlestick protocol, it is not the first or most relevant priority for meningococcal exposure.
The best answer is C, as the work furlough from day 10 to day 21 after exposure addresses the specific risk of meningococcal disease following a needlestick injury. This aligns with CBIC's focus on timely intervention and work restriction to prevent transmission in healthcare settings. Prophylactic antibiotics (e.g., rifampin) should also be considered, but the question asks for the exposure management, and furlough is a primary control measure. Hepatitis B and TB considerations are secondary and managed separately.
CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain III:
Prevention and Control of Infectious Diseases, which includes protocols for managing exposure to communicable diseases like meningococcal infection.
CBIC Examination Content Outline, Domain IV: Environment of Care, which addresses work restrictions and exposure management.
CDC Guidelines for Meningococcal Disease Prevention and Control (2023), which recommend work furlough and monitoring for exposed healthcare workers.
NEW QUESTION # 94
An infection preventionist is observing the cleaning and disinfection process of semi-critical devices. To ensure these items have been reprocessed meeting the minimum requirements, which of the following is required?
Answer: B
Explanation:
The Certification Study Guide (6th edition) emphasizes that thorough cleaning is the most critical step in the reprocessing of all reusable medical devices, including semi-critical devices (those that contact mucous membranes or nonintact skin). A foundational requirement is that initial cleaning begins as soon as possible after use. Prompt cleaning prevents organic material-such as blood, secretions, and tissue-from drying on device surfaces and within lumens, which can shield microorganisms and significantly reduce the effectiveness of subsequent disinfection.
The study guide explains that delayed cleaning increases the risk of biofilm formation and makes removal of soil more difficult, potentially compromising patient safety. For this reason, point-of-use pre-cleaning and rapid transport to reprocessing are considered minimum expectations. Cleaning must occur before any high- level disinfection or sterilization; without effective cleaning, even correctly selected disinfectants may fail.
The other options are incorrect or misleading. There is no universal requirement for detergents with pH lower than 7; detergent selection should follow manufacturer instructions. Waiting 24 hours before cleaning is contrary to best practice and increases risk. Soaking devices in liquid chemical sterilants for extended periods does not address the prerequisite of cleaning and may not be appropriate for semi-critical devices unless specified by the manufacturer.
This question reflects a key CIC exam principle: timely cleaning is non-negotiable and is the cornerstone of safe device reprocessing.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 10: Cleaning, Sterilization, Disinfection, and Asepsis.
NEW QUESTION # 95
......
First and foremost, we have high class operation system so we can assure you that you can start to prepare for the CIC exam with our study materials only 5 to 10 minutes after payment. Fortunately, you need not to worry about this sort of question any more, since you can find the best solution in this website--our CIC Training Materials. With our continued investment in technology, people and facilities, the future of our company has never looked so bright. There are so many advantages of our CIC practice test and I would like to give you a brief introduction now.
Learning CIC Mode: https://www.actualtorrent.com/CIC-questions-answers.html
BTW, DOWNLOAD part of ActualTorrent CIC dumps from Cloud Storage: https://drive.google.com/open?id=1nhHoHtpgTlJKxGIEAumvvw0xRez4J37E