BTW, DOWNLOAD part of FreeDumps EFM dumps from Cloud Storage: https://drive.google.com/open?id=1povH23U8ytPwECDfBrsTxEOuGj04iIi_
Once the user has used our EFM test prep for a mock exercise, the product's system automatically remembers and analyzes all the user's actual operations. The user must complete the test within the time specified by the simulation system, and there is a timer on the right side of the screen, as long as the user begins the practice of EFM quiz guide, the timer will run automatic and start counting. If the user does not complete the mock test question in a specified time, the practice of all EFM valid practice questions previously done by the user will automatically uploaded to our database. The system will then generate a report based on the user's completion results, and a report can clearly understand what the user is good at. Finally, the transfer can be based on the EFM Valid Practice Questions report to develop a learning plan that meets your requirements. With constant practice, users will find that feedback reports are getting better, because users spend enough time on our EFM test prep.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Fetal Assessment and Methods | 9% | - Indications for monitoring - Correlation with clinical status - Auxiliary assessment techniques |
| Topic 2: Professional Issues | 5% | - Legal and ethical aspects - Documentation standards - Safety and quality improvement |
| Topic 3: Electronic Monitoring Equipment | 5% | - Troubleshooting artifacts - Proper application and use - Calibration and accuracy |
| Topic 4: Pattern Recognition and Intervention | 70% | - Fetal heart rate patterns classification - Clinical decision-making and interventions - Interpretation per NICHD standards - Tracing evaluation and management |
| Topic 5: Physiology | 11% | - Fetal cardiovascular physiology - Uteroplacental function - Factors affecting fetal oxygenation |
We provide a wide range of learning and preparation methodologies to the customers for the NCC EFM complete training. After using the NCC EFM exam materials, success would surely be the fate of customer because, self-evaluation, highlight of the mistakes, time management and sample question answers in comprehensive manner, are all the tools which are combined to provide best possible results. EFM Exam Materials are also offering 100% money back guarantee to the customers in case they don't achieve passing scores in the EFM exam in the first attempt.
NEW QUESTION # 121
(Full question statement)
Recurrent decelerations are defined as occurring with 50% or more of contractions in any window of how many minutes?
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
According to the NCC C-EFM Content Outline and AWHONN Fetal Heart Monitoring Principles, recurrent decelerations are specifically defined as decelerations that occur with #50% of uterine contractions in a
20-30-minute window, but standardized interpretation guidelines used by NCC and ACOG categorize recurrent patterns based on any 30-minute evaluation period.
AWHONN (FHM 6th Ed.) explains that fetal heart patterns must be evaluated over "a sufficiently long segment, typically 30 minutes, to determine whether the pattern is intermittent or recurrent." Menihan & Simpson further emphasize that recurrent decelerations imply a persistent physiologic stressor, requiring systematic evaluation and intrauterine resuscitation. NCC's Candidate Guide ties this rule directly into categorization within Category II and III tracings. Therefore, 30 minutes is the correct standard evaluation interval for determining recurrence.
NEW QUESTION # 122
A 30-year-old woman (G2P0) is experiencing preterm labor at 26-weeks gestation. She is receiving magnesium sulfate for neuroprotection. Her external fetal monitoring tracing over the past 30 minutes is shown. The next step would be to: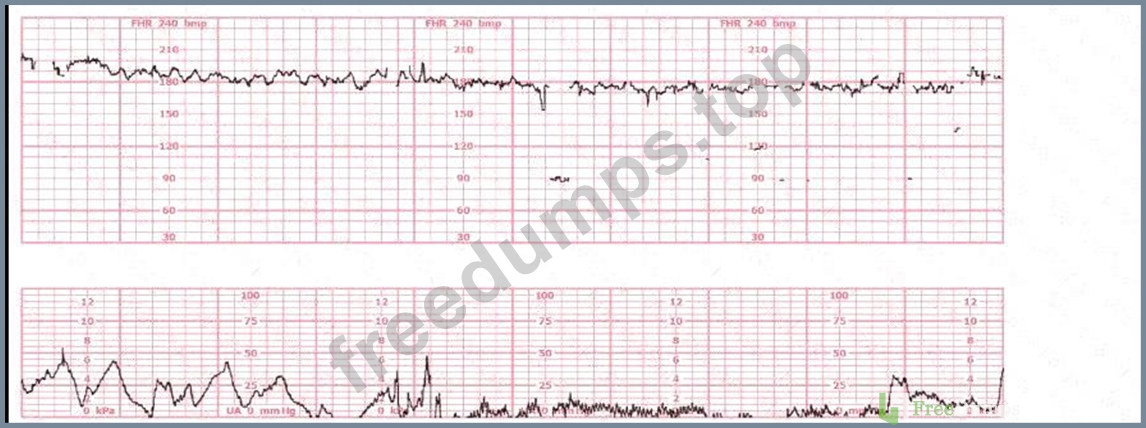
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline ~170-175 bpm # fetal tachycardia
* Minimal variability
* No contractions of significance
* Maternal treatment with magnesium sulfate, which typically decreases baseline and variability-not increase it NCC and AWHONN physiology guidelines emphasize that fetal tachycardia is most commonly associated with maternal infection, including chorioamnionitis, especially in preterm labor.
Magnesium sulfate does not cause tachycardia; it generally causes:
* # baseline
* # variability
Thus, fetal tachycardia + minimal variability in a preterm patient strongly suggests maternal infection, requiring evaluation for chorioamnionitis.
Why the wrong answers are incorrect:
* A. Acetaminophen # used after confirming fever, not before evaluating the cause.
* B. Discontinuing magnesium # magnesium sulfate does not cause tachycardia; discontinuing it removes fetal neuroprotection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Simpson & Creehan; Menihan EFM; Creasy & Resnik.
NEW QUESTION # 123
This fetal heart rate tracing represents: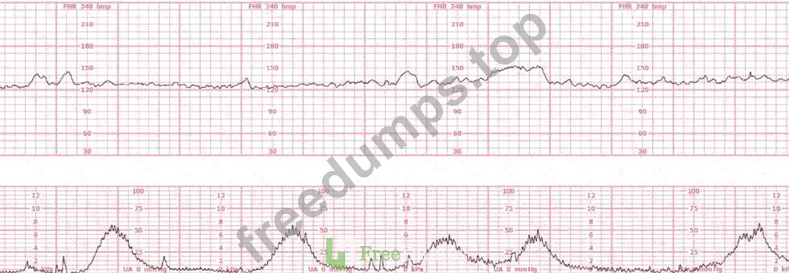
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The lower uterine tracing shows a repetitive contraction pattern characterized by pairs of contractions occurring close together, followed by a longer interval. This is known as "uterine contraction coupling." Key features confirming coupling:
* Two contractions occur back-to-back, separated by only a few seconds.
* Then a longer rest period occurs before the next pair.
* This pattern persists over several minutes.
* FHR remains normal with moderate variability and no decelerations.
Coupling is a uterine activity pattern, not a fetal heart rate abnormality.
Why the other answers are incorrect
A). Category I tracing
* While the FHR itself may appear reassuring, the question is explicitly about the pattern shown, which is (per NCC classification) a uterine pattern, not a category designation.
C). Prolonged acceleration
* A prolonged acceleration would be a fetal heart rate increase #15 bpm lasting #2 minutes but <10 minutes.
* No such FHR increase appears on the strip.
Thus, the correct interpretation is B. Coupling of contractions.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Pocket Guide; Menihan; Simpson & Creehan.
NEW QUESTION # 124
Interventions undertaken to address fetal tachycardia are targeted at maximizing
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Fetal tachycardia is typically caused by maternal fever, dehydration, hypoxia, medications, infection, or fetal stress. AWHONN and Simpson & Creehan emphasize that management focuses on improving oxygen delivery across the placenta, which is governed by uteroplacental perfusion.
Menihan's EFM text states that "interventions for fetal tachycardia must address oxygen transfer by optimizing uteroplacental blood flow," including hydration, reducing uterine activity, maternal repositioning, and treating maternal fever.
Increasing maternal circulation alone is insufficient unless it improves placental blood flow. Enhancing fetal sympathetic tone is not a clinical goal and would worsen tachycardia.
Creasy & Resnik highlight that fetal heart rate abnormalities resolve when uteroplacental perfusion is restored, confirming this as the primary target of intervention.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 125
Sustained fetal supraventricular tachycardia that goes untreated is most likely to result in:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Sustained fetal supraventricular tachycardia (SVT) often produces heart rates > 200-240 bpm, causing:
* Poor ventricular filling
* Decreased stroke volume
* Reduced cardiac output
* Congestive heart failure
* Progressive fluid accumulation
NCC and AWHONN emphasize that untreated SVT leads to hydrops fetalis, characterized by:
* Ascites
* Pleural effusion
* Pericardial effusion
* Skin edema
Why the other answers are incorrect:
* A. Fetal anemia - Causes tachycardia but is not caused by SVT.
* C. Neonatal pacemaker - Pacemakers treat heart block, not SVT.
Correct answer: B. Hydrops fetalis
References:NCC C-EFM Candidate Guide; AWHONN Principles & Practices; Simpson & Creehan; Creasy
& Resnik Maternal-Fetal Medicine.
NEW QUESTION # 126
......
The chance of making your own mark is open, and only smart one can make it. We offer EFM exam materials this time and support you with our high quality and accuracy EFM learning quiz. Comparing with other exam candidates who still feel confused about the perfect materials, you have outreached them. So it is our sincere suggestion that you are supposed to get some high-rank practice materials like our EFM Study Guide.
Valid EFM Exam Forum: https://www.freedumps.top/EFM-real-exam.html
What's more, part of that FreeDumps EFM dumps now are free: https://drive.google.com/open?id=1povH23U8ytPwECDfBrsTxEOuGj04iIi_