BONUS!!! Download part of SurePassExams EFM dumps for free: https://drive.google.com/open?id=1cWszvqAudDMjRMFTrswCqxQdTmb4ewIj
As long as you buy our EFM practice materials and take it seriously consideration, we can promise that you will pass your EFM exam and get your certification in a short time. We can claim that if you study with our EFM Guide quiz for 20 to 30 hours, you will be confident to pass the exam for sure. So choose our exam braindumps to help you review, you will benefit a lot from our EFM study guide.
| Section | Weight | Objectives |
|---|---|---|
| Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
SurePassExams presents its Certified - Electronic Fetal Monitoring (EFM) exam product at an affordable price as we know that applicants desire to save money. To gain all these benefits you need to enroll in the Certified - Electronic Fetal Monitoring EXAM and put all your efforts to pass the challenging Certified - Electronic Fetal Monitoring (EFM) exam easily. In addition, you can test specs of the Certified - Electronic Fetal Monitoring practice material before buying by trying a free demo. These incredible features make SurePassExams prep material the best option to succeed in the NCC EFM examination. Therefore, don't wait. Order Now !!!
NEW QUESTION # 101
(Full question statement)
A woman at 39-weeks gestation is in labor, progressing normally. The baseline fetal heart rate has increased from 125 to 150 beats per minute over the last hour with moderate variability. What is the next step?
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC-recommended references (Simpson, AWHONN FHM, Creasy & Resnik) note that baseline increases within the normal range (110-160 bpm) accompanied by moderate variability are typically benign. Mild physiologic causes-maternal activity, fetal stimulation, or normal sympathetic activation-may transiently raise baseline FHR.
AWHONN stresses that intervention is required only when tachycardia exceeds 160 bpm or when variability is minimal/absent or accompanied by recurrent decelerations.
Here, the baseline increase to 150 bpm remains within normal limits and is paired with moderate variability, which the NCC recognizes as the strongest indicator of adequate fetal oxygenation.
Therefore, evaluation is complete, and continued observation is the appropriate course.
NEW QUESTION # 102
This tracing reflects: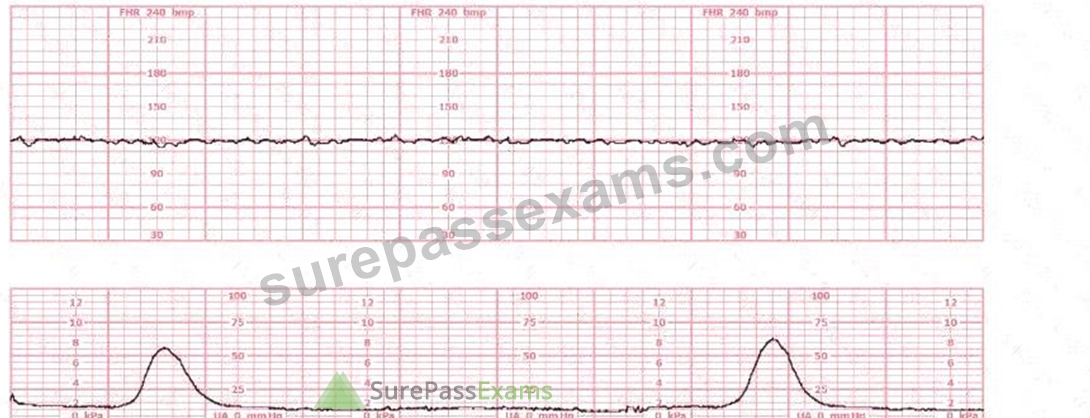
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
In NCC C-EFM interpretation, classification of a fetal heart tracing is based on NICHD's three-tier system:
Category I, II, and III. Category III represents an abnormal tracing requiring immediate evaluation and prompt intervention.
Key findings in this tracing:
* Baseline:Baseline is approximately 140 bpm, within the normal range (110-160 bpm).Baseline alone does not determine category.
* Variability:The tracing shows absent variability:
* No beat-to-beat oscillations
* Flat, minimal fluctuationNICHD and NCC define absent variability as amplitude range undetectable.
* Accelerations:No accelerations are present.
* Decelerations:The strip does not show decelerations or bradycardia.However, absent variability alone with no accelerations for 20 minutes is highly concerning.
Category Classification per NICHD/NCC:
Category III criteria include ANY of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
Also recognized as Category III:
* Persistent absent variability lasting #20 minutes with no accelerations, which is strongly suggestive of fetal acidemia when sustained.
This tracing shows:
* Absent variability (flat line)
* No accelerations
* Persisting over an extended period
Under NCC and AWHONN guidance:
A persistently flat tracing must be classified as Category III unless proven otherwise (e.g., fetal sleep, maternal medications), and it requires immediate intrauterine resuscitation and evaluation for potential expedited delivery.
Why Category I is NOT correct:
Category I requires:
* Moderate variability
* No late or variable decelerationsThis tracing does not have moderate variability.
Why Category II is NOT correct:
Category II includes minimal variability, marked variability, intermittent variables/lates, absence of accelerations after stimulation.
This tracing is worse than Category II because variability is absent, not minimal.
Thus, the tracing fits Category III.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 103
This is a fetal heart rate tracing of a multiparous woman whose cervix is 7 cm dilated on admission. The most likely cause for this pattern is: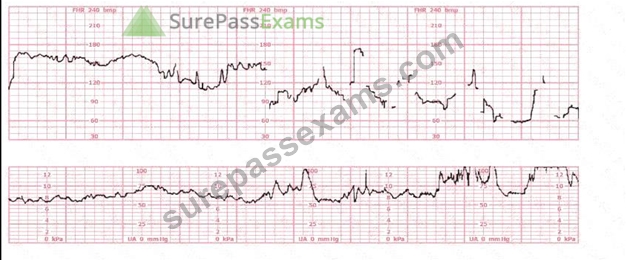
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows a clear relationship between uterine activity and fetal heart rate changes:
* The uterine activity strip demonstrates very frequent contractions with little resting time between them, exceeding five contractions in 10 minutes, averaged over a 30-minute window.
* NCC and NICHD define tachysystole as "more than 5 contractions in 10 minutes, averaged over 30 minutes, regardless of whether the labor is spontaneous or stimulated." As uterine activity intensifies and becomes excessively frequent, the fetal heart rate strip begins to show:
* Progressive decrease in baseline
* Recurrent decelerations with gradual onset and recovery
* Reduced variability in the latter portion of the strip
This pattern is consistent with uteroplacental insufficiency caused by excessive uterine activity (tachysystole). NCC and AWHONN emphasize that tachysystole can result in decreased uterine blood flow and fetal oxygenation, leading to late or prolonged decelerations and eventual bradycardia if not corrected.
Why the other options are less likely:
* A. Placental abruptionTypically associated with maternal symptoms (pain, vaginal bleeding, firm
/boardlike uterus) and often a sustained increase in resting tone or a hypertonic contraction, not simply very frequent contractions. These maternal findings are not described in the vignette.
* B. Rapid fetal descentUsually causes variable or early decelerations related to head compression, but the tocodynamometer would not necessarily show this degree of contraction frequency. The lower strip here clearly highlights excessive contractions as the primary problem.
Thus, the tracing's FHR abnormalities are best explained by tachysystole, making C. Tachysystole the most appropriate answer.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline - Pattern Recognition and Intervention; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 104
A 30-year-old woman (G2P0) is experiencing preterm labor at 26-weeks gestation. She is receiving magnesium sulfate for neuroprotection. Her external fetal monitoring tracing over the past 30 minutes is shown. The next step would be to: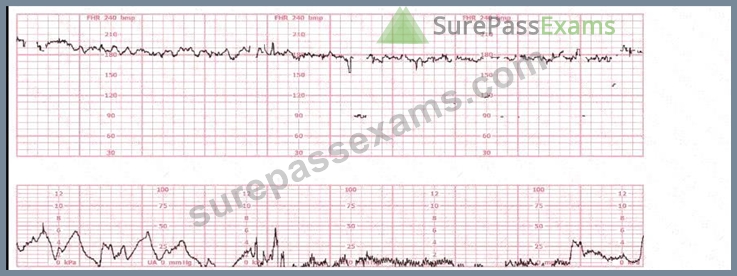
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline ~170-175 bpm # fetal tachycardia
* Minimal variability
* No contractions of significance
* Maternal treatment with magnesium sulfate, which typically decreases baseline and variability-not increase it NCC and AWHONN physiology guidelines emphasize that fetal tachycardia is most commonly associated with maternal infection, including chorioamnionitis, especially in preterm labor.
Magnesium sulfate does not cause tachycardia; it generally causes:
* # baseline
* # variability
Thus, fetal tachycardia + minimal variability in a preterm patient strongly suggests maternal infection, requiring evaluation for chorioamnionitis.
Why the wrong answers are incorrect:
* A. Acetaminophen # used after confirming fever, not before evaluating the cause.
* B. Discontinuing magnesium # magnesium sulfate does not cause tachycardia; discontinuing it removes fetal neuroprotection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Simpson & Creehan; Menihan EFM; Creasy & Resnik.
NEW QUESTION # 105
A woman is admitted at 41-weeks gestation for fetal evaluation following a motor vehicle accident. She reports that she hit her abdomen on the steering wheel. The underlying physiology of the tracing is most likely: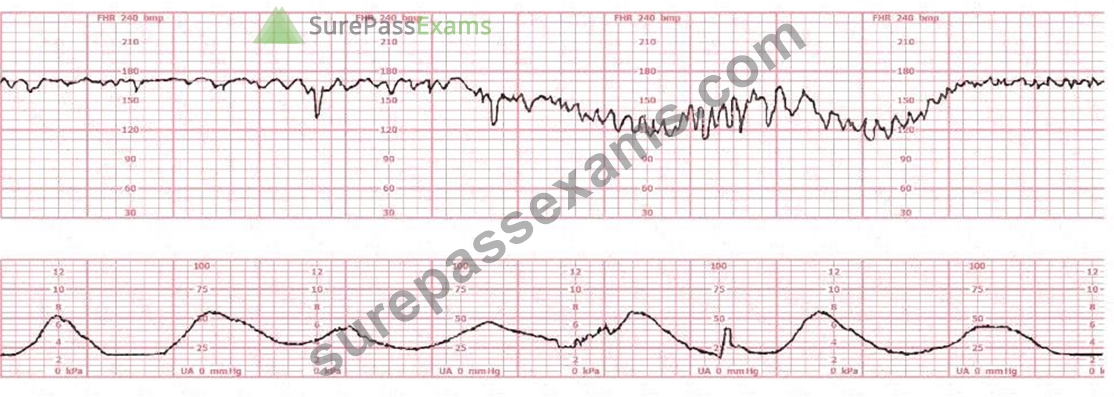
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing shows recurrent late decelerations, decreased variability, and subtle baseline shifts-findings that strongly correspond to uteroplacental insufficiency. In trauma cases, NCC emphasizes that placental abruption is the most common fetal complication, caused by shearing forces separating the placenta from the uterine wall.
Key physiologic points per NCC/AWHONN/Menihan:
* Maternal blunt abdominal trauma frequently leads to partial or concealed abruption.
* Abruption produces decreased uteroplacental blood flow, resulting in:
* Late decelerations
* Minimal/absent variability
* Baseline shifts or instability
Cord accident (option A) typically produces variable decelerations, not late-pattern decelerations.
Fetal trauma (option B) is extremely rare and does not produce a consistent deceleration pattern.
Thus, the physiology most consistent with this tracing and mechanism of injury is placental abruption.
References:NCC C-EFM Candidate Guide (2025); NCC Physiology Domain; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 106
......
If you master our EFM quiz torrent and pass the exam it proves that you have excellent working abilities and can be suitable for a good job. You will earn a high salary in a short time. Besides, you will get a quick promotion in a short period because you have excellent working abilities and can do the job well. You will be respected by your colleagues, your boss, your relatives, your friends and the society. All in all, buying our EFM Test Prep can not only help you pass the exam but also help realize your dream about your career and your future.
New EFM Test Guide: https://www.surepassexams.com/EFM-exam-bootcamp.html
DOWNLOAD the newest SurePassExams EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1cWszvqAudDMjRMFTrswCqxQdTmb4ewIj